
Pediatric Robotic Surgery
Also covered as: esophageal atresia
Educational content from recorded physician discussions — not medical advice. Always talk to your child's care team about your child's situation.
Content of this collection
Surgical Management
1 item
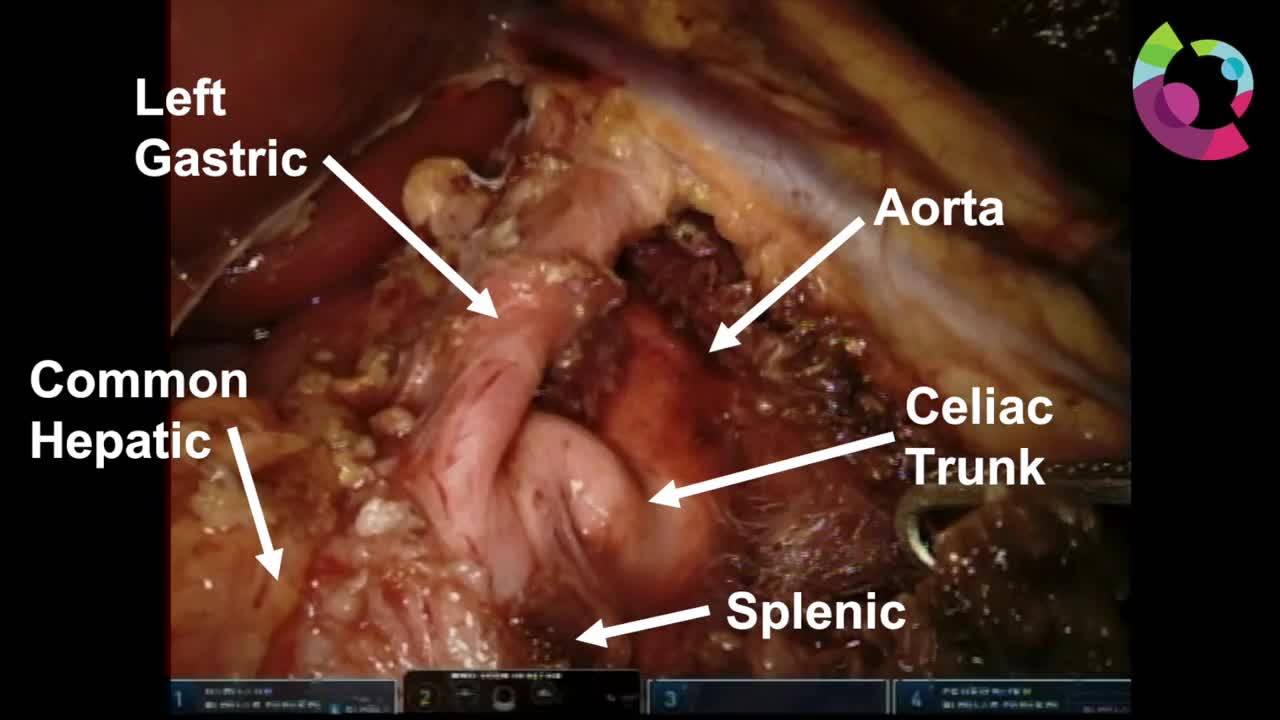
Robotic-Assisted Release of the Median Arcuate Ligament for Pediatric MALS
Watch →
Presented by Alejandra M Casar Berazaluce, MD; Alexander Gibbons, MD; and Jaimie D Nathan, MD from Cincinnati Children's Hospital Medical Center at the IPEG - International Pediatric Endosurgery Group 28th Annual Congress for Endosurgery in
video4:51 · Mar 2019
Evidence & Research
2 items

Comparison of robotic versus thoracoscopic repair for congenital esophageal atresia
Watch →
New article you should know by Cecilia Gigena
"Comparison of robotic versus thoracoscopic repair for congenital esophageal atresia: a propensity score matching analysis "
Authors: Mengxin Zhang, Jinshi Huang, Wei Zhong, Xi Zhang, Yin
video0:56 · Feb 2024
Johana Sosa Jurado, MD - Best of the Best in Pediatric Surgery 2024
Watch →
Watch IBEROMERICANA's Dr. Johana Sosa Jurado's presentation on “Epidemiological study of pediatric robotic surgery at Carlos Andrade Marín Hospital” at the 2024 Best of the Best in Pediatric Surgery event!
Moderators: Todd Ponsky, Cecili
video5:38 · Feb 2024
Case-Based Learning
1 item
Heat 1 Winner: Dariusz Patkowski, MD, PhD - Best of the Best in Pediatric Surgery 2024
Watch →
Watch the voting from the first heat!
Presentations from heat one:
Prof. Shilpa Sharma: Exploring alternative pathway of stem cell proliferation for hepatic regeneration by partial liver resection in extra hepatic biliary atresia.
video2:30 · Feb 2024
In-Depth Reviews
3 items


Dr. Marc Michalsky - Pediatric Robotic-Assisted Surgery – Developing a Programmatic Paradigm
Watch →
Marc Michalsky, MD, MBA, FACS, FAAP, FASMBS - Pediatric Robotic-Assisted Surgery – Developing a Programmatic Paradigm
Surgical Grand Rounds (October 29, 2025)
video66:48 · Oct 2025
Colorectal Quiz: Episode 50 - 16th Annual European Pediatric Colorectal and Pelvic Reconstruction Conference, Stockholm, Sweden, October 2025 - What did we learn?
Listen →
In this special 50th episode of the Colorectal Quiz Podcast, Dr. Marc Levitt and an international panel including Filipa Jalles, MD, Lindsey Clarke, PA-C and Meghan Mesa, BSN, RN, CPN review key takeaways from the 16th European Pediatric Co
podcast24:17 · Mar 2026
Update Course Rewind 2025: Robotics in Pediatric Surgery: Which indications benefit the most?
Watch →
This video series recaps highlights from the 13th Annual Pediatric Surgery Update Course. Dr. Juan Gurria discusses the pros and cons of robotic surgery in pediatric patients, comparing it to laparoscopic surgery, and exploring its future.
video4:35 · Jun 2026
Summaries and takeaways+ Show
Summary of this collection+ Show
Key points, with the moment each was said+ Show
Featured picks for families are being prepared — the summaries above are written for you.
Takeaways+ Show
Robotic surgery in pediatrics has matured from niche adoption to routine practice across multiple specialties. The da Vinci SI-to-XI transition was transformational, enabling enhanced range of motion and flexibility . High-volume centers now perform 130–140 robotic cases annually, with general surgery matching or exceeding urology . Approximately 12% of cases occur in patients <15 kg, driven primarily by urology , though equipment improvements now permit surgery in children <10 kg . The learning curve favors robotics: proficiency requires 10–15 cases versus 20–30 for laparoscopy , and operative times drop rapidly—sleeve gastrectomy learning curves fell from 132 minutes (SI) to 36 minutes (XI) . Wristed instruments enable facile suturing in confined spaces like the pelvis [e2959-c20, e6928-c19], and articulating needle drivers prove especially helpful in complex anastomoses [e2936-c6, e6861-c6]. Clinical outcomes are favorable: no difference in complications or readmissions for sleeve gastrectomy regardless of BMI , and lower anastomotic strictures and readmissions in esophageal atresia repair compared to thoracoscopy [e7940-c5, e7940-c6]. Robotic surgery reduces postoperative pain, infection risk, and surgeon fatigue while improving depth perception [e12230-c3, e12230-c10, e12230-c11]. Conversion rates to open surgery are lower than laparoscopy in colorectal cases , and oncologic results are comparable [e12230-c14, e12230-c18]. Emerging technologies include ICG fluorescence for vascular assessment [e2959-c21, e11653-c8], digital overlay systems integrating axial imaging , and modular platforms with 5 mm instruments . Cost concerns are mitigating: robotic expenses approach equivalence with other techniques , and no insurance denials have been attributed to robotic surgery at high-volume centers .
- Robotic proficiency requires half the cases of laparoscopy (10–15 vs. 20–30), with operative times dropping rapidly after initial learning curve.
- Wristed instruments and 3D visualization enable complex anastomoses and suturing in confined spaces, particularly beneficial in pelvic and reconstructive procedures.
- Robotic esophageal atresia repair shows lower anastomotic strictures and unplanned readmissions versus thoracoscopy; outcomes in bariatric and colorectal surgery match laparoscopy.
- Equipment advances permit surgery in patients <10 kg; ~12% of high-volume center cases occur in patients <15 kg, primarily urologic.
- ICG fluorescence reduces leak/ischemia risk in pull-throughs; emerging platforms offer 5 mm instruments, modular designs, and CT-overlay navigation.
For patients & families
Robotic surgery uses computer-controlled instruments that give surgeons more precise movement and better views inside the body than traditional tools [e12230-c2, e12230-c10]. Doctors discussed using this technology for many types of operations in children, including procedures on the intestines, urinary system, and bile ducts [e12230-c19, e12230-c22]. The robotic arms can bend and rotate in ways that help surgeons work in tight spaces, which is especially helpful when operating on smaller children [e11169-c2, e6866-c6]. Several hospitals shared their experiences: one center grew from about 70 robotic cases in 2014 to over 130 per year by 2020 . Doctors reported that children typically go home within a few days after robotic procedures, with good recovery [e2936-c9, e6928-c25]. The technology appears safe when used by trained surgeons, though the instruments are currently too large for newborns . Studies comparing robotic to traditional keyhole surgery found that robotic cases may have fewer complications in some procedures, though they can take longer at first while the surgical team is learning [e7940-c5, e12230-c5]. Costs have been decreasing as the technology becomes more common .
Robotic surgery uses computer-controlled instruments that give surgeons more precise movement and better views inside the body than traditional tools [e12230-c2, e12230-c10]. Doctors discussed using this technology for many types of operations in children, including procedures on the intestines, urinary system, and bile ducts [e12230-c19, e12230-c22]. The robotic arms can bend and rotate in ways that help surgeons work in tight spaces, which is especially helpful when operating on smaller children [e11169-c2, e6866-c6]. Several hospitals shared their experiences: one center grew from about 70 robotic cases in 2014 to over 130 per year by 2020 . Doctors reported that children typically go home within a few days after robotic procedures, with good recovery [e2936-c9, e6928-c25]. The technology appears safe when used by trained surgeons, though the instruments are currently too large for newborns . Studies comparing robotic to traditional keyhole surgery found that robotic cases may have fewer complications in some procedures, though they can take longer at first while the surgical team is learning [e7940-c5, e12230-c5]. Costs have been decreasing as the technology becomes more common .
The doctors in this collection+ Show
All expert statements+ Show
Every expert statement below comes from the recorded discussions, with its speaker and moment.
Colorectal Quiz: Episode 50 - 16th Annual European Pediatric Colorectal and Pelvic Reconstruction Conference, Stockholm, Sweden, October 2025 - What did we learn?
Many centers are starting irrigation competency even with an ostomy in place, particularly for total colonic Hirschsprung patients who may have delayed takedown
clinicalLindsay Clark1:17 ↗
Enterocolitis remains a risk for Hirschsprung patients even after pull-through at about a rate of 20% of all patients
epidemiological2:13 ↗
Regular irrigations minimize enterocolitis risk
clinical2:21 ↗
Total colonic Hirschsprung patients represent the highest risk group for enterocolitis
clinicalMarc Levitt2:45 ↗
Most centers still do some kind of crusting, putting stool on the bottom first while patients have a stoma for small periods of time to help get their bottom used to it
clinicalMegan Misa3:35 ↗
Betel leaf was used for peristomal skin protection in Bangladesh with pristine skin results
clinicalMegan Misa4:11 ↗
Diet and nutrition management is not one size fits all; families must identify individual food triggers through pattern recognition
clinicalLindsay Clark4:48 ↗
There have been advances in robotic-assisted repair for Hirschsprung disease and use of ICG to check blood supply of pull-throughs
clinicalFelipe Gli5:23 ↗
ICG fluorescence imaging can reduce the risk of leaks and ischemia during pull-throughs
clinical5:36 ↗
High frequency ultrasound measurement of muscle internal thickness can help determine the segment of aganglionic bowel
clinicalFelipe Gli5:49 ↗
More surgeons are able to perform robotic surgery on children less than 10 kg because equipment is improving
clinicalMarc Levitt6:44 ↗
Robotic surgery expenses have become almost equivalent to other techniques
clinicalFelipe Gli6:51 ↗
Goblet cells increase from proximal to distal bowel, producing more mucus distally which has a protective role
clinicalMarc Levitt7:40 ↗
The more proximal bowel that needs to be resected, the more at risk the patient is for future enterocolitis because proximal segments don't make as much protective mucus
clinicalMarc Levitt7:56 ↗
Mechanical stress and distension on the bowel wall leads to increased gut microbial dysbiosis and breakdown in mucosal lining and barrier function
clinicalMarc Levitt8:37 ↗
Bowel wall stress shows upregulation of pro-inflammatory factors affecting immune response, contributing to enterocolitis
clinicalMarc Levitt9:04 ↗
Most pull-through decompensation occurs despite originally good pathology, due to inadequate post-operative management
clinicalMarc Levitt9:39 ↗
Aggressive management with laxatives when needed and Botox when needed prevents pull-through decompensation
clinicalMarc Levitt9:52 ↗
The perineal-preserving PSARP avoids perineal body dissection altogether and avoids dehiscence possibility
clinicalMarc Levitt16:25 ↗
Perineal-preserving PSARP could potentially avoid colostomies and colostomy closures in many patients
opinionMarc Levitt16:36 ↗
PRAA (posterectal advancement anoplasty) involves mobilization of posterior rectal wall only in males with perineal fistula and some females with perineal fistula when the fistula is in the anteriormost extent of the sphincteric ellipse
clinicalMarc Levitt16:57 ↗
In vestibular fistula repair, surgeons do not need to dissect all the way to the areolar plane separating anterior rectum from posterior vagina; they only need to ensure no tension on the rectum during anoplasty
clinicalMarc Levitt17:18 ↗
Delaying vaginal reconstruction in cloaca may allow for other surgical options with less conflict and avoid bowel vaginoplasty
clinicalFelipe Gli18:07 ↗
A vaginal replacement can hold the spot in the perineum and be resected later when the patient is older
clinicalFelipe Gli18:27 ↗
Cloaca patients need long-term follow-up especially during puberty to avoid menstrual obstruction, incapacity for egress, and risk of endometriosis and damage to uterus and fallopian tubes
clinicalFelipe Gli18:44 ↗
Structures that look atretic may actually grow into real useful structures, supporting a strategy of waiting on Mullerian structures
clinicalMarc Levitt19:24 ↗
A bowel neovagina can bridge the gap when native vagina does not reach, and may be removable in the future when native vagina can be pulled through after puberty
clinicalMarc Levitt19:50 ↗
Removal of the skin tag in chronic anal fissure can lead to better long-term healing
clinicalFelipe Gli21:02 ↗
Injection of 20 to 50 units of Botox can improve healing in chronic anal fissure
clinicalFelipe Gli21:02 ↗
There is a higher incidence of perianal disease in children with Crohn's disease, and sometimes perianal disease can be the first hint that the patient will develop Crohn's disease
clinicalMarc Levitt21:35 ↗
What's new+ Show