
Fetal Surgery
Also covered as: congenital diaphragmatic hernia · myelomeningocele · pulmonary hypoplasia · hydrops · ascites · bronchial atresia · urethral atresia · oligohydramnios
Educational content from recorded physician discussions — not medical advice. Always talk to your child's care team about your child's situation.
Content of this collection
Diagnosis & Workup
3 items

Overview of Prenatal Diagnosis: Cincinnati Fetal Center
Watch →
Dr. Mark P. Johnson, research chair in fetal therapy, discusses an overview of prenatal diagnosis of fetal lower urinary tract obstruction. Dr. Johnson describes the most common causes of lower urinary tract obstructions, progressive oligoh
video40:34 · Nov 2018
Prenatal diagnosis of fetal lower urinary tract obstruction: Fetal...
Watch →
Dr. Mark P. Johnson, research chair in fetal therapy, discusses an overview of prenatal diagnosis of fetal lower urinary tract obstruction. Dr. Johnson describes the most common causes of lower urinary tract obstructions, progressive oligoh
video40:14 · Jan 2019
Utility of Fluorescence In Situ Hybridization as a Fetal Surgery Eligibility Criterion for....
Watch →
Lizzy Lee from Cincinnati Children's discusses a pertinent study on the utility of invasive genetic testing, specifically Fluorescence In Situ Hybridization (FISH), prior to fetal surgery. The research questions whether FISH provides additi
video0:52 · Jun 2026
Surgical Management
17 items


Controversies in Congenital Diaphragmatic Hernia: Update Course 2018
Watch →
At the 6th Annual Pediatric Surgery Update Course, Dr. Mark Wulkan discusses controversies in congenital diaphragmatic hernia including advantages of open versus minimally invasive repair (with visualization of technique), timing of CDH rep
video41:42 · Sep 2018
Urologic Fetal Intervention: Cincinnati Fetal Center
Watch →
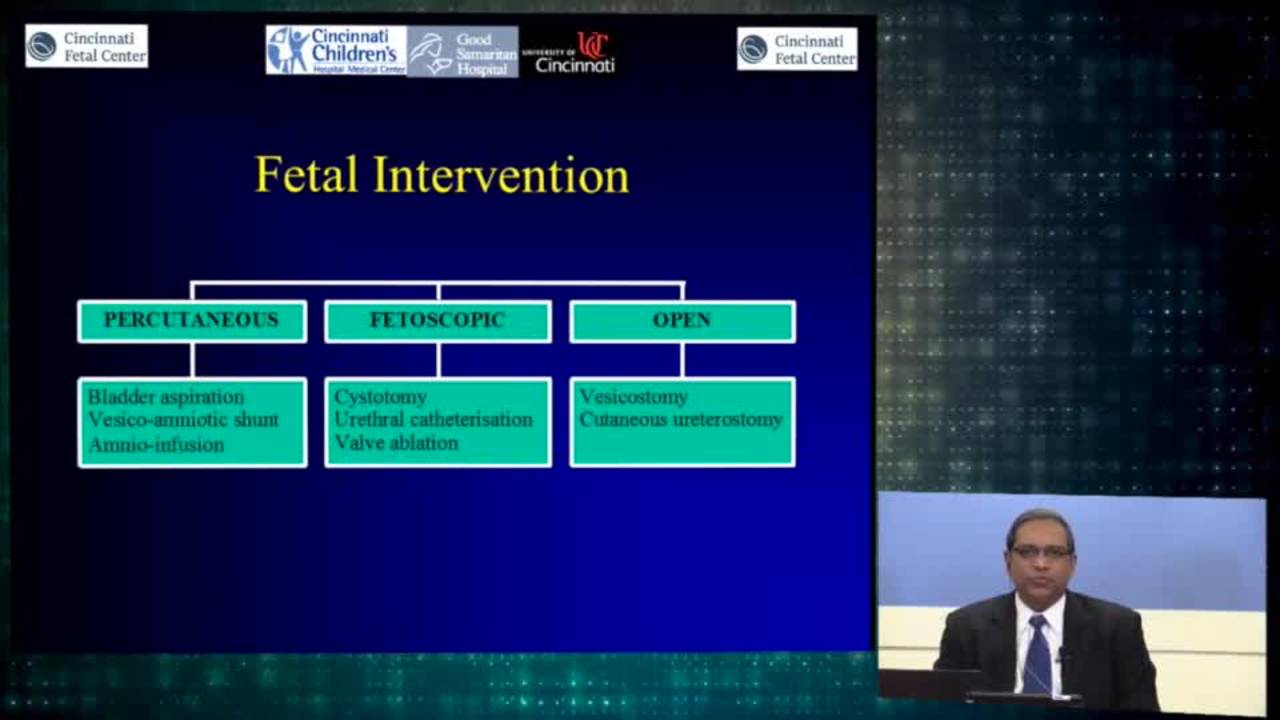
Dr. Pramod Reddy, Division of Pediatric Urology, discusses fetal cystoscopy. Dr. Reddy discusses fetal intervention and risks, urinary tract obstructions, open intervention versus fetoscopic intervention, the risks of shunt usage for renal
video61:40 · Nov 2018
Fetal Interventions Part II: Lung Lesions
Watch →
Dr. Alan Flake leads a discussion in fetal interventions for prenatally-diagnosed lung lesions.
video16:30 · Jan 2019
Pediatric Hernia: Update Course 2013
Watch →
During the first annual Stay Current in Pediatric Surgery Update Course in 2013, Dr. Peter Mattei, general, thoracic and fetal surgery, of The Children's Hospital of Philadelphia, discusses hernia management. Topics of discussion include in
video52:50 · Jan 2019
Fetal urological aspect: Fetal Genitourinary Disease 2015
Watch →
Dr. Pramod Reddy discusses fetal cystoscopy, includingfetal intervention and risks, urinary tract obstructions, open intervention versus fetoscopic intervention, the risks of shunt usage for renal functions, normal fetal fluid pressure rang
video59:23 · Jan 2019
Fetoscopic endoluminal tracheal occlusion and twin-twin transfusion: Fetal...
Watch →
Dr. Yan Deprest, Professor of Obstetrics GYN, University Hospitals Gasthuisberg. Leuven, Belgium, discusses fetoscopic endoluminal tracheal occlusion. His presentation provides insight on the percutaneous procedure, trocar insertion, delive
video149:16 · Jan 2019
Open Fetal Surgery Overview: Fetal Surgery 2012
Watch →
Dr. Flake, attending surgeon and director of the General Surgery Fellowship Program at The Children's Hospital of Philadelphia,presents a brief overview of open fetal surgery. Topics discussed include the prenatal diagnosis of an abnormal f
video37:55 · Jan 2019
Lung Lesions: Fetal Interventions Parts I+II
Watch →
Dr. Alan Flake leads a discussion in fetal interventions for prenatally-diagnosed lung lesions.
video30:56 · Jan 2019
Fetal Interventions Part I: Lung Lesions
Watch →
Dr. Alan Flake leads a discussion in fetal interventions for prenatally-diagnosed lung lesions.
video14:27 · Jan 2019
Prenatal Management of CPAMs: Lung Lesions
Watch →
Dr. Alan Flake discusses prenatal management of congenital pulmonary airway malformations (CPAMs). It includes two videos of examples of fetal surgery.
video18:16 · Jan 2019
Neonatal Lung Lesions with Dr. Steven Rothenberg
Listen →
Dr. Steven Rothenberg discusses Newborn Lung Lesions with Dr Todd Ponsky. Edited by Ian C. Glenn, MD & Nicholas E. Bruns, MDPrenatal evaluationPatients with prenatal diagnosis of cystic lung lesions are referred for prenatal evaluation and
podcast66:58 · Dec 2020
Fetoscopic Endoluminal Tracheal Occlusion (FETO)
Listen →
Did you know that we can do surgery on a fetus? In today's episode, we hear from Dr. Foong-Yen Lim, M.D. about Fetoscopic Endoluminal Tracheal Occlusion or FETO to treat Congenital Diaphragmatic Hernia (CDH) with Host Rod Gerardo, M.D.
podcast5:54 · Jul 2021
Fetoscopic Repair of Myelomeningocele (MMC)
Listen →
Continuing our series on Fetal Surgery, today's episode reviews the basics of fetoscopic repair of myelomeningocele with Dr. Foong-Yen Lim, M.D. Host: Rod Gerardo
podcast5:52 · Aug 2021
Treatment for Long Gap Esophageal Atresia: Esophageal Elongation and Replacement
Listen →
Pediatric surgeons Dr. Daniel Von Allmen and Dr. Todd Ponsky from Cincinnati children's Hospital discussing the technique for treating long gap esophageal atresia. For additional info please visit: https://www.youtube.com/c/CincinnatiChildr
podcast10:56 · Jan 2022
Myelomeningoceles (open spina bifida) -Fetoscopic Intrauterine Myelomeningocele Closure
Watch →
In this educational video from Lurie Children’s Hospital, Dr. Robin Bowman walks us through a fetoscopic intrauterine myelomeningocele (MMC) closure, a cutting-edge surgical intervention for open neural tube defects diagnosed in utero.Key H
video3:41 · Dec 2025
Inside a FETO Procedure: Fetoscopic Balloon Tracheal Occlusion with Dr. Beth Rymeski
Watch →
This video, featuring Dr. Beth Rymeski from Cincinnati Children's, details the procedural aspects of Fetoscopic Endoluminal Tracheal Occlusion (FETO). It explains how a fetoscope is used to insert and inflate a balloon in the fetal trachea,
video4:30 · Jul 2026
Inside a FETO Procedure: Fetoscopic Balloon Tracheal Occlusion with Dr. Beth Rymeski
Watch →
This video, presented by Dr. Beth Rymeski of Cincinnati Children's Hospital, details the procedural aspects of Fetal Endoluminal Tracheal Occlusion (FETO). It explains how a fetoscope is used to insert a balloon into the fetal trachea to te
video4:30 · Jul 2026
Evidence & Research
7 items



Fetal Surgical Intervention for Myelomeningocele: Fetal Surgery 2012
Watch →
Dr. Adzick is the surgeon-in-chief and director of the Center for Fetal Diagnosis and Treatment at The Children’s Hospital of Philadelphia (CHOP). He gives his presentation on myelomeningocele (MMC), the most severe form of spin bifida. Top
video165:47 · Jan 2019
Journal of Pediatric Surgery Article Review: January 2022 APSA Issue
Listen →
We're back with the January issue of JPS article highlights. This time we're talking to editor Dr. Cassandra Kelleher and authors Drs. Gail Besner, Shahrazad Joharifard and Sarah Stokes with Dr. Todd Ponsky. Hosts: Ellen Encisco, Em Tombash
podcast13:09 · Feb 2022
Update Course 2021: TOP PUBLICATIONS IN NON - PED SURG JOURNALS
Watch →
Dr. Jose Campos and his team, Sociedad Chilena Cirugia Pediatrica curate the best pediatric surgical articles in non-core pediatric surgery journals and in this session, they describe their 5 favorites from the past year. The conversation i
video22:13 · May 2022
Journal of Pediatric Surgery Article Highlights: April 2022
Listen →
We're back with the April issue of JPS article highlights. This time we're talking to Dr. Paul Tam and authors Dr. Natalie Lopyan and Dr. Christina Theodorou. Hosts: Em Tombash, Rod Gerardo, Brittany Levy Lopyan NM, Perrone EE, Gadepalli SK
podcast8:38 · Jul 2022
Update Course 2022 - APSA PDC UPDATES - Mary Edwards, Paul Jeziorczak, Craig Lillehei, and Charles Snyder,
Watch →
In this session, members of the APSA Professional Development Committee (PDC) discussed the latest top articles and practice updates. We were joined by Drs. Mary Edwards, Paul Jeziorczak, Craig Lillehei, and Charles Snyder.
Topics discus
video64:30 · Sep 2022
Tracheomalacia and tracheomegaly in infants and children with congenital diaphragmatic hernia managed with and without fetoscopic endoluminal tracheal occlusion (FETO): a multicentre, retrospective cohort study
Watch →
David Basurto, Kanokwaroon Watananirun, Anne-Gael Cordier, Juan Otaño, Diane Carriere, Marianna Scuglia, Anna Moraes de Luna Freire Vargas, Jordi Prat, Francesca Maria Russo, Anne Debeer, Cleisson Fábio Andrioli Peralta, Paolo De Coppi, Edu
video0:59 · Oct 2024
Quick Literature Updates Ep 19
Watch →
We’re back with nineteenth episode of "Quick Literature Updates" the podcast series that delivers the latest updates in pediatric surgery literature in a quick and digestible format. In each episode, we review articles covering the most int
video4:27 · May 2025
In-Depth Reviews
2 items


The Full Story on CPAMs
Listen →
Here we cover Congenital Pulmonary Airway Malformations (CPAMs) through a story with the help of Dr. Todd Ponsky, Dr. Pam Choi, Dr. Beth Rymeski, Dr. Jacob Langer, and Dr. Steven Rothenberg. Hosts: Ellen Encisco & Rod GerardoChapter 1: Pren
podcast56:08 · Sep 2021
Open Fetal Surgery & EXIT Procedure with Dr. Jose Peiro
Watch →
Join us for an insightful discussion with Dr. Jose Peiro, pediatric surgeon and director of endoscopic fetal surgery at Cincinnati Children’s Fetal Care Center, which is the highest-volume fetoscopic center in the nation. Dr. Peiro walks us
video10:23 · Oct 2024
Emerging & Future Directions
1 item

The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
Watch →
Lizzy Lee from Cincinnati Children's discusses a pivotal review on 'The Fetal Frontier,' highlighting emerging therapies for genetic diseases. This video explores the innovative approaches of treating genetic conditions in the womb, leverag
video0:44 · May 2026
Summaries and takeaways+ Show
Summary of this collection+ Show
Key points, with the moment each was said+ Show
Featured picks for families are being prepared — the summaries above are written for you.
Takeaways+ Show
Current state of fetal surgery: The field encompasses a narrow set of accepted indications—primarily twin-twin transfusion syndrome (TTTS), severe congenital diaphragmatic hernia (CDH), myelomeningocele (MMC), and select lung lesions—with most congenital defects still managed postnatally . TTTS laser photocoagulation achieves 92–94% survival of at least one twin and 75–88% dual survival in stages 1–3, with careful vascular mapping critical to avoid missed anastomoses [e1025-c9, e1025-c11, e9231-c11]. For severe left CDH (lung-to-head ratio ≤25%), fetal endoscopic tracheal occlusion (FETO) increases survival from 8–15% to 40–60%, though preterm rupture of membranes and tracheomalacia (typically resolving by 55 months) are recognized sequelae [e1025-c1, e5404-c11, e9334-c2, e9334-c7]. The MOMS trial established that open prenatal MMC repair halves shunt dependency (40% vs. 82%) and doubles independent ambulation (42% vs. 21%), with recent registry data showing uterine dehiscence reduced to 3.7% through refined technique [e1026-c34, e1026-c35, e10241-c10]. Fetoscopic MMC repair—via percutaneous or laparoscopy-assisted approaches—permits vaginal delivery and achieves comparable hindbrain reversal with delivery at 37 weeks, though long-term motor outcomes await rigorous comparison [e10241-c13, e10241-c14, e9984-c18].
Lung lesions and technical evolution: Congenital pulmonary airway malformations (CPAMs) with cyst volume ratio >1.6 carry high hydrops risk, but maternal betamethasone now rescues >50% of cases, rendering open fetal lobectomy exceedingly rare (<1 case per 5 years at major centers) [e1027-c6, e1027-c7, e1027-c8, e884-c8]. Macrocystic lesions may require thoracoamniotic shunting (70–75% survival), and EXIT procedures—though historically overused—remain reserved for CVR >2 with compressive physiology [e1027-c12, e1088-c2]. Bronchial atresia and extra-lobar sequestrations are more refractory to steroids and carry higher intervention risk [e1027-c10, e1027-c14]. For lower urinary tract obstruction (LUTO), vesico-amniotic shunting improves pulmonary outcomes but not renal function; fetoscopic laser ablation of posterior urethral valves offers etiologic diagnosis and more physiologic drainage, achieving 55% two-year survival with 73% of survivors retaining normal renal function [e6024-c36, e6024-c38]. Serial amnioinfusion with lactated Ringer's (volume = GA×10 mL) sustains lung development in renal-failure fetuses, with 88% birth survival and 70% neonatal survival in early series, though 20% chorioamnionitis risk mandates vigilance [e6017-c22, e6017-c27, e6017-c36].
- TTTS laser achieves 88–94% survival of ≥1 twin; complete ablation in <5 min and careful AA-anastomosis mapping minimize donor loss and neurologic injury (5–6% major delays). [e1025-c9, e1025-c10, e1025-c19]
- FETO for severe CDH (LHR ≤25%, liver-up) raises survival from 8–20% to 40–60%; tracheomalacia occurs in 5% more cases but resolves by 55 months. Delivery ≥32 wk yields 60% survival. [e1025-c1, e1025-c17, e9334-c1, e9334-c2]
- Prenatal MMC repair halves shunt need (40% vs. 82%) and doubles walking (42% vs. 21%). Modern open technique: 3.7% dehiscence, 5% PPROM; fetoscopic: 37-wk delivery, >50% vaginal. [e1026-c34, e1026-c35, e10241-c10, e10241-c13]
- Maternal betamethasone rescues >50% of CPAM with CVR >1.6; open fetal lobectomy now <1/5 yr at high-volume centers. Macrocystic lesions: shunt if hydrops (70–75% survival). [e1027-c7, e1027-c8, e1027-c11, e1027-c12]
- LUTO: vesico-amniotic shunt protects lungs but not kidneys; fetoscopic laser ablation of PUV achieves 55% 2-yr survival, 73% normal renal function in survivors. Serial amnioinfusion (GA×10 mL): 88% birth survival, 20% chorioamnionitis. [e6024-c36, e6024-c38, e6017-c22, e6017-c27, e6017-c36]
For patients & families
Fetal surgery addresses serious conditions detected before birth, aiming to improve outcomes by intervening during pregnancy rather than waiting until delivery. Doctors use ultrasound and sometimes MRI to diagnose problems like spina bifida (an opening in the spine), lung masses, diaphragm defects, or blockages in the urinary system. Some conditions can be treated through small incisions using tiny cameras and instruments (fetoscopy), while others require opening the uterus more fully. For spina bifida, repairing the opening before birth can reduce the need for brain fluid drainage tubes by half and improve the baby's ability to walk. When a baby's airway is blocked by a mass, doctors can deliver the head while keeping the umbilical cord attached to maintain oxygen supply, giving time to secure the airway safely. For severe diaphragm defects that prevent lung growth, temporarily blocking the windpipe with a tiny balloon encourages the lungs to develop, improving survival from around 15% to 40%. Most lung masses actually shrink on their own late in pregnancy and don't require surgery before birth. Fetal surgery carries risks including early delivery, membrane rupture, and the need for cesarean delivery in this and future pregnancies. Families meet with a team of specialists—surgeons, kidney doctors, neonatologists, and social workers—to understand the diagnosis, treatment options, and what to expect after birth.
Fetal surgery addresses serious conditions detected before birth, aiming to improve outcomes by intervening during pregnancy rather than waiting until delivery. Doctors use ultrasound and sometimes MRI to diagnose problems like spina bifida (an opening in the spine), lung masses, diaphragm defects, or blockages in the urinary system. Some conditions can be treated through small incisions using tiny cameras and instruments (fetoscopy), while others require opening the uterus more fully. For spina bifida, repairing the opening before birth can reduce the need for brain fluid drainage tubes by half and improve the baby's ability to walk. When a baby's airway is blocked by a mass, doctors can deliver the head while keeping the umbilical cord attached to maintain oxygen supply, giving time to secure the airway safely. For severe diaphragm defects that prevent lung growth, temporarily blocking the windpipe with a tiny balloon encourages the lungs to develop, improving survival from around 15% to 40%. Most lung masses actually shrink on their own late in pregnancy and don't require surgery before birth. Fetal surgery carries risks including early delivery, membrane rupture, and the need for cesarean delivery in this and future pregnancies. Families meet with a team of specialists—surgeons, kidney doctors, neonatologists, and social workers—to understand the diagnosis, treatment options, and what to expect after birth.
The doctors in this collection+ Show
All expert statements+ Show
Every expert statement below comes from the recorded discussions, with its speaker and moment.
Utility of Fluorescence In Situ Hybridization as a Fetal Surgery Eligibility Criterion for....
Many centers require genetic testing to rule out chromosome abnormalities before fetal surgery, even when ultrasounds and blood tests already look reassuring
clinicalLizzie Lee0:09 ↗
A study reviewed nearly 1000 pregnancies evaluated for fetal surgery
epidemiologicalLizzie Lee0:23 ↗
When imaging and cell-free DNA screening showed low risk for aneuploidy, the FISH test matched those results 100% of the time
clinicalLizzie Lee0:23 ↗
For low-risk pregnancies, FISH did not provide any new information that changed surgery candidacy
clinicalLizzie Lee0:36 ↗
In carefully selected low-risk cases, non-invasive screening may be enough, potentially avoiding the FISH procedure
opinionLizzie Lee0:42 ↗
Inside a FETO Procedure: Fetoscopic Balloon Tracheal Occlusion with Dr. Beth Rymeski
FETO is a percutaneous intervention on the mother using one trocar placed through the maternal abdominal wall into the uterus
clinicalBeth Rymeski0:33 ↗
The procedure uses a standard fetoscope with a side channel through which the balloon is worked
clinicalBeth Rymeski0:42 ↗
The goal of FETO is to allow fluid to stay in the lungs and allow the lungs to expand and grow
clinicalJill Knepprath0:47 ↗
FETO helps prevent pulmonary hypoplasia, which is a big factor in poor outcomes for CDH babies
clinicalJill Knepprath0:53 ↗
The tongue is an easy landmark when doing FETO because it is bumpy
clinicalBeth Rymeski1:21 ↗
Fluid is hooked up to the scope and can be intermittently turned on and off to push tissue away from the scope to allow easier advancement
clinicalBeth Rymeski1:29 ↗
If the baby's head is not perfectly in alignment with the scope, twisting and turning is required to navigate through the mouth
clinicalBeth Rymeski1:38 ↗
The epiglottis is a key landmark to identify when navigating to find the correct location
clinicalBeth Rymeski1:58 ↗
Excessive torquing of the membranes should be avoided because the scope goes through the abdominal wall and uterine wall, and excessive turning can cause membrane damage
clinicalBeth Rymeski2:23 ↗
The scope should always be advanced until the carina is visualized, which confirms tracheal (not esophageal) placement and indicates position within the trachea
clinicalBeth Rymeski2:36 ↗
The balloon should not be driven into one side of the trachea or the other; it should inflate in the main trachea
clinicalBeth Rymeski2:56 ↗
The scope is backed up as the balloon is inflated so that balloon inflation can be watched
clinicalBeth Rymeski3:03 ↗
The balloon is filled with water, around 0.65 to 0.8 mL, depending on the size of the trachea
clinicalJill Knepprath3:08 ↗
The balloon contains a little metal ball that can be visualized
clinicalBeth Rymeski3:29 ↗
Sometimes the trocar advances into the mouth during the procedure and needs to be backed out
clinicalBeth Rymeski3:33 ↗
Final confirmation requires advancing the scope one more time to verify the balloon is below the vocal cords and in the main trachea
clinicalJill Knepprath3:40 ↗
FETO is a percutaneous intervention on the mother using one trocar placed through the abdominal wall into the uterus
clinicalBeth Rymeski0:33 ↗
The procedure uses a standard fetoscope with a side channel through which the balloon is worked
clinicalBeth Rymeski0:42 ↗
The goal of FETO is to allow fluid to stay in the lungs and allow the lungs to expand and grow
clinicalJill Knepprath0:47 ↗
FETO helps prevent pulmonary hypoplasia, which is a big factor in poor outcomes for CDH babies
clinicalJill Knepprath0:53 ↗
The tongue is an easy landmark during FETO because it is bumpy
clinicalBeth Rymeski1:21 ↗
Fluid is hooked up to the scope and can be intermittently turned on and off to push tissue away and allow easier advancement
clinicalBeth Rymeski1:29 ↗
If the baby's head is not perfectly aligned with the scope, twisting and turning is required to navigate through the mouth
clinicalBeth Rymeski1:38 ↗
The epiglottis is sought as a landmark to guide navigation
clinicalBeth Rymeski1:58 ↗
Excessive torquing of the membranes should be avoided because the scope goes through the abdominal and uterine walls and could cause membrane damage
clinicalBeth Rymeski2:23 ↗
What's new+ Show