
Thoracoscopic Repair of Esophageal Atresia with Distal Tracheo-esophageal...
Part of
Esophageal Atresia 40 items
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
Thoracoscopic Repair of Tracheo-esophageal Fistula Tricks: Pediatric Surgery...
19 min · Published Jul 2017
Video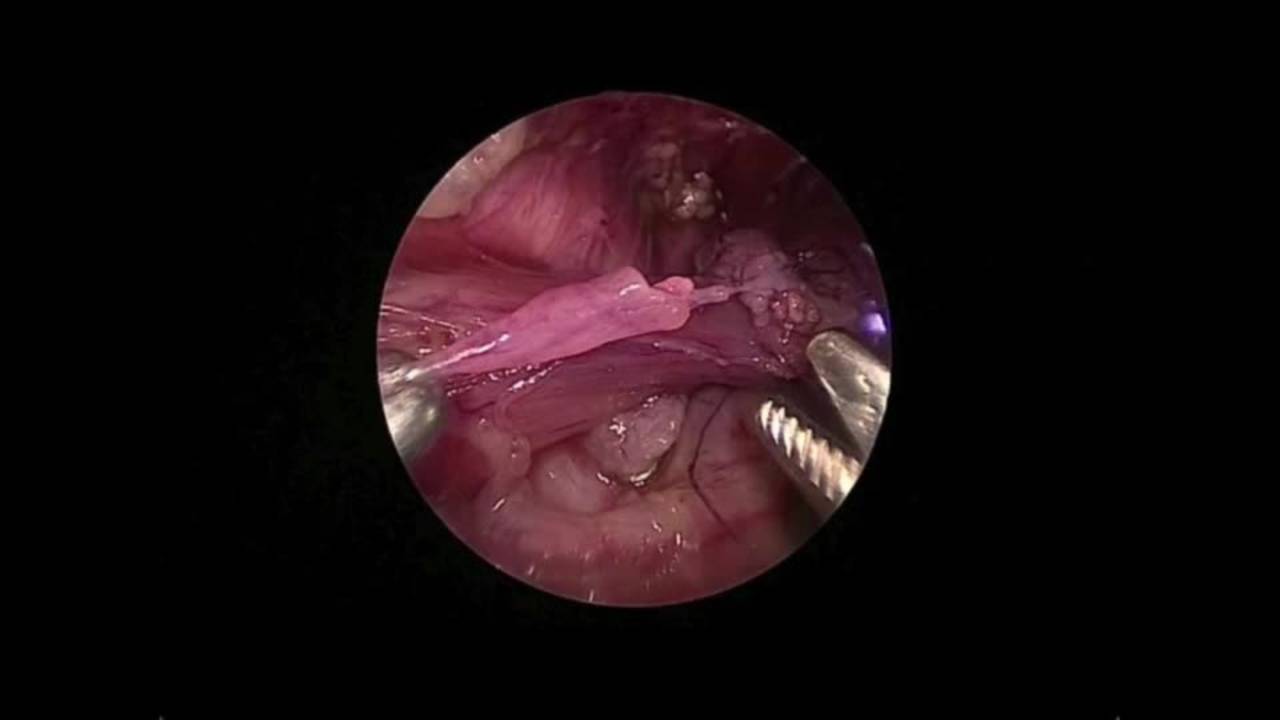
EA/TEF Discussion & Technique: Difficult Cases
19 min · Published Dec 2013
Video
Comparison of robotic versus thoracoscopic repair for congenital esophageal atresia
56 s · Published Feb 2024
Video
Tips and Tricks: EA & TEF
Dr. Steve Rothenberg · 9 min · Published Dec 2012
Podcast
Case Based Journal Review: Esophageal Atresia in 2022
17 min · Published Aug 2022
Video
Thoracoscopic TEF Repair, Is It Really Better Than Open? Update Course 2018
18 min · Published Aug 2018
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
The patient is a term male newborn with esophageal atresia and distal tracheoesophageal fistula.
Patient positioning is left lateral decubitus with the arm extended and restrained, with a roll under the left axilla.
Division of the azygous vein typically leads the surgeon to the fistula site.
The azygous vein can be divided with an energy device, simply coagulated, or double clipped and divided.
Thoracoscopic magnification allows for excellent delineation of the trachea and esophagus.
The fistula is ligated with a suture ligature flush with the trachea but not divided initially to prevent the distal esophagus from retracting.
Asking the anesthesiologist to push on the nasoesophageal tube aids in dissection of the proximal esophageal stump.
The esophagus is often quite adherent to the trachea and may even share a common wall, requiring careful dissection.
Dissection can be continued to the thoracic inlet, resulting in excellent mobilization of the proximal esophagus.
The fistula is divided a few millimeters distal to the ligature to liberate the distal esophagus.
Following fistula division, the ligature should be tested with 25 to 30 centimeters water positive pressure ventilation.
The back wall anastomosis is completed first using interrupted 4-0 or 5-0 absorbable sutures.
Extracorporeal knot tying was used in this case because the two ends came together nicely with minimal tension.
Sutures are placed 2 to 3 millimeters apart, with 5 to 6 sutures usually sufficient to complete the posterior wall anastomosis.
The nasoesophageal tube is advanced to protect the posterior wall prior to starting the anterior wall anastomosis.
It is important to take full thickness bites of healthy esophageal wall and mucosa with each suture.
Fewer sutures are usually required for the anterior wall anastomosis compared to the posterior wall.
A chest tube was placed in this case, but this is no longer routinely used.