
Renal transplantation: Fetal Genitourinary Disease 2015
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about end-stage renal disease
same diagnosisVideo
Fetal urological aspect: Fetal Genitourinary Disease 2015
59 min · Published Jul 2017
Video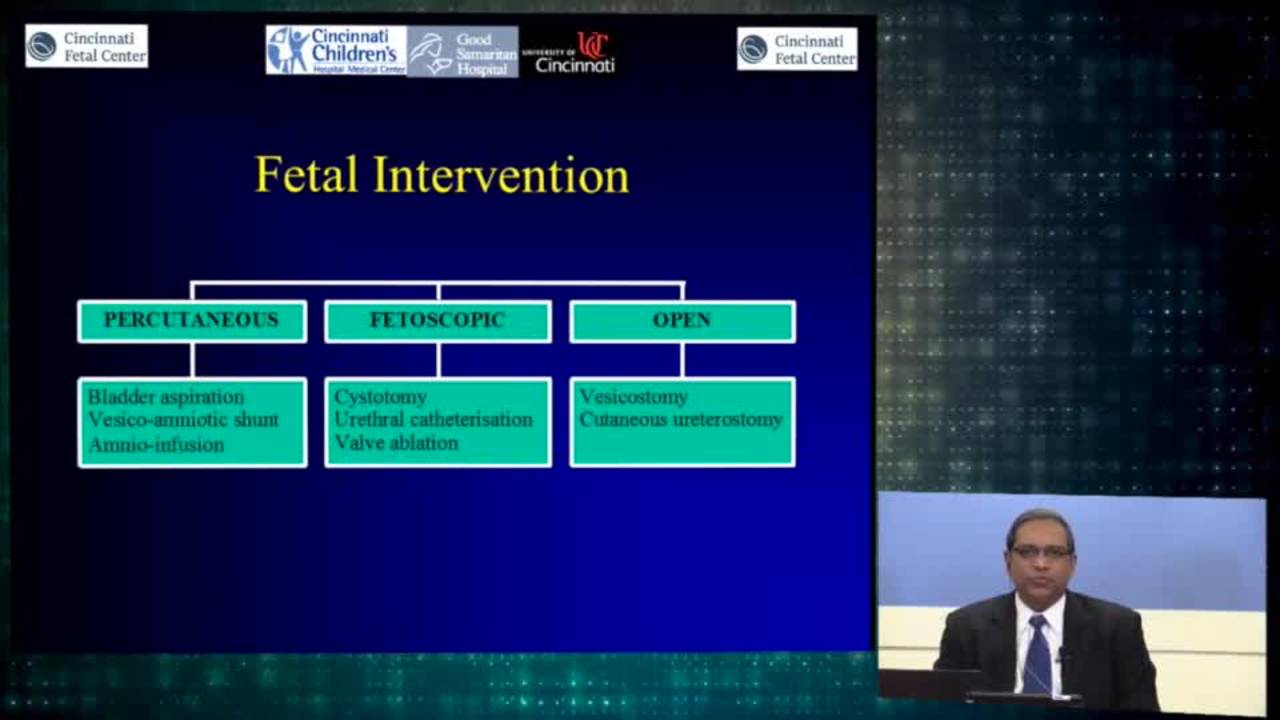
Urologic Fetal Intervention: Cincinnati Fetal Center
61 min · Published Nov 2018
Video
Urologic intervention: Cincinnati Fetal Center
28 min · Published Nov 2018
Podcast
Fetal and Newborn Management of Cloacal Malformations
13 min · Published Sep 2026
Video
Cloaca - Urologic Concerns
25 min · Published Nov 2018
Podcast
Coagulopathy and Analgesia
45 min · Published Oct 2019
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
Infants who make urine are not likely to need peritoneal dialysis immediately but will likely need it in the future
When placing both G-tube and PD catheter together, the PD catheter should be left alone for a couple of weeks if possible
Gastrostomy tube placement should focus on the lesser curvature to preserve the stomach for potential future bladder augmentation
Hemodialysis catheters need to be fairly large caliber and placement should stay as much as possible to the right internal jugular site because that is a straight shot into the atrium
Inguinal and umbilical hernias can develop when babies are on peritoneal dialysis
If hernias are not affecting the mechanics of dialysis and not particularly symptomatic, they tend to be left alone
The ideal weight for infant renal transplant is around 10 kg if not on PD
Infants on PD can be transplanted closer to 8 kg because they have a more accommodating abdominal cavity and laxity in the abdominal wall
All infant recipients have been transplanted with adult donors
An extraperitoneal approach is used for infant renal transplantation with an incision extending to the upper edge close to the costal margin
The biggest complication from a general surgical perspective in infant renal transplants are wound complications as opposed to vascular complications
Some infants can only have skin closed initially and develop leaks or dehiscence requiring biologic mesh (such as derma matrix) for closure
In a 13-year follow-up of G-tubes in babies, they all migrate up onto the chest
Placing G-tube too close to PD catheter creates infection risk early on because there is not enough space between sites and drainage can get underneath the PD catheter dressing
Standard G-tube insertion site is 2 finger breadths below the costal margin
In small babies, G-tube should be placed 3 or 4 finger breadths below costal margin because it will rise up with growth
G-tube location should be high up on the stomach towards lesser curvature to allow ability to use gastric segment for gastric augmentation later in life
Some babies with posterior urethral valves will need urinary diversion with vesicostomy about 1-2 finger breadths below the umbilicus, requiring G-tube placement away from this site to mitigate infection risk
PD catheters can be placed to allow immediate use with lower volumes rather than waiting 3-7 days
Amnioinfusions are performed when patients present for first imaging to assess the baby's capacity to swallow and see if the stomach fills
In fetal imaging, bladder and bladder wall thickness and isthmus are always measured
Early onset large bladders that extend up and push the diaphragm and stomach back may cause anatomic distortion that results in stomachs ending up higher long term
Many babies with bladder outlet obstruction have small stomachs, possibly related to minimum amniotic fluid during development