
Gastroschisis: Advanced Practice Providers
hosted by Dr. Todd Ponsky & Dr. Em Gootee · StayCurrentMD
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
Abdominal Wall Defects: Update Course 2013
37 min · Published Sep 2013
Video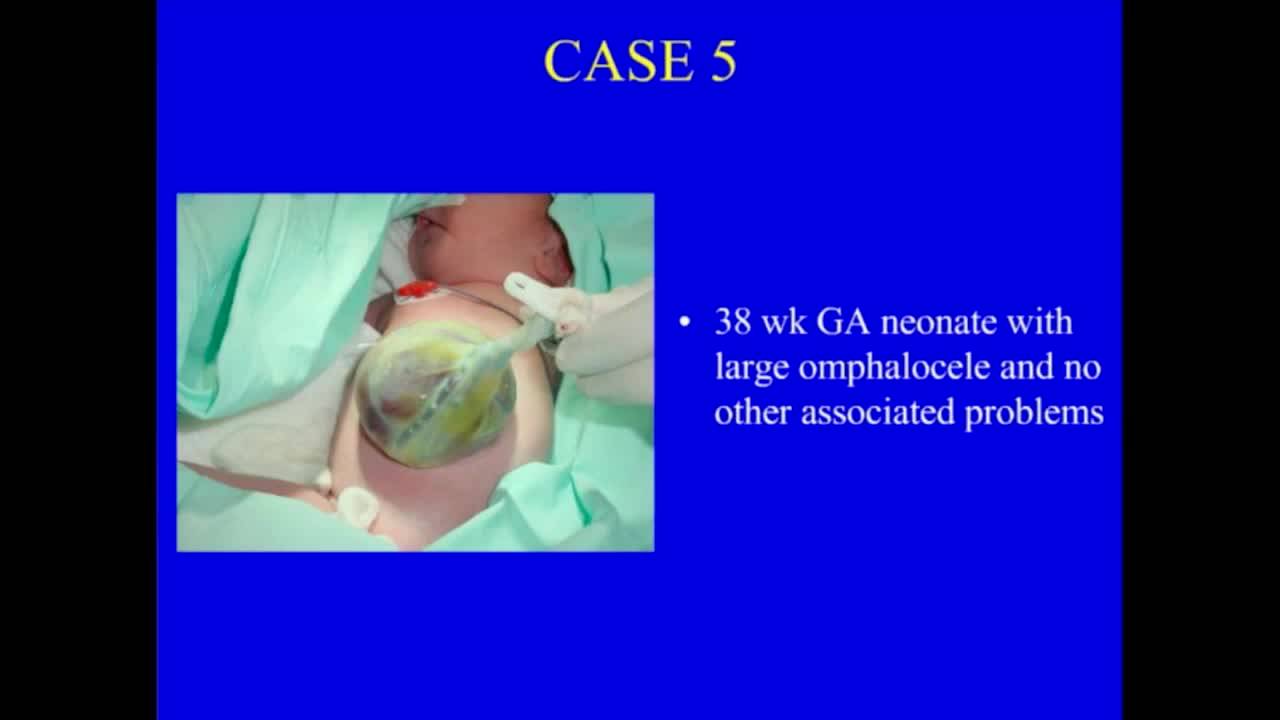
Abdominal Wall Defects
37 min · Published Nov 2018
Video
Staged Closure of Gastroschisis with Spring-loaded Silo
27 min · Published Feb 2020
Video
Staged Closure of Gastroschisis with Spring-loaded Silo
27 min · Published Feb 2020
Video
Multidisciplinary Approach: Intestinal Failure Innovations
97 min · Published Dec 2014
Video
Intestinal Rehabilitation, Episode 4: Surgical Management, Part 1
CCHMC Pediatric Surgery · 19 min · Published Oct 2022
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
The abdominal wall forms around the 4th week of gestation, well before most women know they are pregnant.
During the 6th week of gestation, rapid growth of intestines and liver expansion causes herniation of the midgut into the umbilical cord.
Around the 10th week of gestation, herniated bowel loops return to the abdominal cavity and the small bowel and colon assume a fixed position.
In gastroschisis, the umbilical cord is located to the left of the defect; in omphalocele it is in the center.
With gastroschisis, bowel is exposed in utero causing it to be thickened, matted, and inflamed; with omphalocele the bowel is covered and remains normal.
Associated anomalies occur in around 10% of gastroschisis cases but 60-75% of omphalocele cases, correlating with increased mortality in omphalocele.
Gastroschisis is herniation of intestinal loops through a full-thickness defect in the anterior abdominal wall, usually lateral to the umbilicus on the right more than the left, around 4 cm in size, with no covering sac.
The etiology of gastroschisis remains unknown. Leading theories propose a vascular event involving the right umbilical vein or right omphalomesenteric artery causing necrosis and abdominal wall weakening.
The incidence of gastroschisis has risen over the last 20 years to as high as 5 per 10,000 live births.
Gastroschisis is associated with young maternal age, prematurity, and low birth weight.
Risk factors for gastroschisis are multifactorial but include young maternal age (<20 years), smoking, and use of vasoconstrictive medications.
Around 90% of gastroschisis cases are diagnosed prenatally on routine ultrasound.
There is no evidence in the literature to support either C-section or vaginal delivery in regards to outcome for gastroschisis.
Initial delivery room management focuses on supporting the infant and keeping the bowel warm and moist: assess airway/breathing/circulation, assess bowel viability, place bowel and lower extremities in bowel bag with intestines central to decrease kinking risk.
Gastroschisis infants experience excessive fluid losses from exposed bowel and require maintenance of temperature >36°C to decrease stress.
An NG or OG tube is placed to decompress the stomach and prevent further intestinal distention in gastroschisis.
There is about a 10% associated occurrence of intestinal atresia with gastroschisis.
Intestinal atresia in gastroschisis can be treated at time of abdominal wall closure with resection and primary anastomosis, or the bowel can be reduced with atresia intact and repaired 4-12 weeks later, possibly requiring temporary ostomy especially with distal atresia.
Surgical management of gastroschisis focuses on safe viscera reduction, identifying and treating associated defects (atresia, perforation), closure of the defect, early recognition of complications, and nutritional support.
Closure is accomplished through either primary surgical closure or staged reduction with silo. Defect size, intestinal condition, and abdominal cavity size impact the decision.
Staged closure with silo is accomplished gradually over 1 to 14 days, then surgically closed either at bedside or in the OR.
At Cincinnati Children's, out of 41 gastroschisis patients in the last 3 years, almost all had staged closures with silos; only a handful with small defects were closed primarily.
Lucille Packard Children's Hospital uses a sutureless technique: silo reduction followed by covering the remaining defect with Mepilex and Tegaderm dressings until fully healed (about 6 weeks), leaving an umbilical hernia that may need later repair.
Todd Ponsky has done only non-sutured gastroschisis repair for the last 6 years and has never had a ventral hernia. He reports 10-20% umbilical hernia rate, most resolving by age 3-5 years, with perfect cosmetic results.
In a pediatric surgery event poll, about 75% of surgeons reported doing non-sutured (Tegaderm) gastroschisis repair.
For non-sutured closure, Todd Ponsky places a silo on all patients, reduces at bedside, and if everything reduces he closes it by tying the umbilical cord with suture, laying it in a circle over the hole, applying gauze and Tegaderm, waiting 4 days, then changing dressing every 4 days until sealed (usually 2 weeks).
Complications of primary gastroschisis closure stem mainly from increased abdominal pressure leading to decreased venous return and possible abdominal compartment syndrome with ischemic injury.
It is important to monitor intra-abdominal pressure during and post gastroschisis closure using bladder pressures, frequent physical exam, urine output monitoring, and assessment of respiratory support requirements.
Literature review shows debate about gastroschisis closure method: some groups report earlier feeding and decreased length of stay with primary closure, others report decreased ventilator time, shorter stay, and lower cost with silo reduction. Overall survival is >95% regardless of closure type.
Post-silo placement nursing care focuses on quick complication recognition: support silo and bowel to avoid kinking/twisting, bowel should be pink with serous (not stool-containing) fluid in bag, monitor lower extremity perfusion, urine output, edema, oxygen requirement, respiratory difficulty, and temperature.
Gastroschisis patients may require as much as 140-150 mL/kg/day of fluids to manage losses.
At Cincinnati Children's, Betadine-soaked gauze is used around the silo base and changed twice daily.
Of all potential gastroschisis complications, dysmotility is the most universal.
Gastroschisis prognosis is mainly dependent on severity of associated problems (prematurity, initial post-op complications) and degree of dysmotility, all impacting course and length of stay.
NEC is reported in about 5-10% of gastroschisis patients, tends to occur later in the course, should be treated same as isolated NEC, and shows no correlation with type of closure performed.
Todd Ponsky does not use bladder pressures for gastroschisis monitoring, finding them not terribly accurate in this patient size. He uses peak airway pressures as primary assessment during reduction, watching them to decide when to stop reducing, and looks at overall baby appearance and urine output.
Dean agrees that bladder pressures are not routinely used; peak airway pressures are very good, or in pressure-control ventilation watch for significant tidal volume changes, plus good physical exam of the belly for tightness.
Jenny emphasizes that in Seattle the majority of gastroschisis care is done by advanced practitioners: non-surgical closure, kids out of ICU within days, then weeks on floors managed by nurse practitioners doing fluid management, feeding advancement, and wound care.
Cincinnati feeding protocol: enteral feedings start 24 hours after NG tube removal (when NG output <20 mL/kg/day for 24 hours), begin at 1 mL/hr, increase by 1 mL/hr daily until day 5, then BID increases, then q8h increases by day 8 if tolerated. PO feedings introduced with windows off tube feeds as tolerated, TPN gradually dialed down.
Cincinnati is enrolling gastroschisis patients in a feeding study randomizing to either the enteral feeding protocol arm or PO ad-lib feedings arm.
Cincinnati data 2010-present: 36 gastroschisis patients required long-term TPN (>30 days). Simple gastroschisis (n=22) averaged 35 days TPN with 3 still on TPN at 1 year. Complex with atresia (n=4) averaged 146 days TPN but all were off TPN on enteral feeds within 10 months.
For gastroschisis monitoring, the volume of NG output matters less than the color: even high-volume clear/spitty output may allow feeding, but any bilious output (regardless of volume) means the patient is not ready to feed.
Studies show about 1/3 of gastroschisis children are below 10th percentile for weight at 1 year but without neurodevelopmental delays at time of evaluation.
Fallon et al 2012 retrospective review reported that gestational age <37 weeks and development of cholestasis were independently linked to poor growth in gastroschisis, whereas small-for-gestational-age or low birth weight was not.
Cincinnati group 2010 outcomes for 71 gastroschisis infants (6 complex) treated with standardized nutritional protocol (2006-2009): enteral feedings started around day 16, median length of stay 42 days, 6 patients discharged on TPN, 24% on tube feedings, rest on oral feeding.
Cincinnati 2006-2008 readmission data (n=58, 21% primary closure, remainder silo): 40% readmitted at least once within first year, >25% of readmissions directly gastroschisis-related. Most common reasons: bowel obstruction, abdominal pain/distention.
Cincinnati readmission analysis found no relationship with place of birth, bowel resection requirement, complex vs simple gastroschisis, small-for-gestational-age, delivery mode, feeding timing, TPN duration, length of stay, gender, maternal age, or prenatal diagnosis.
Cincinnati data showed interesting trend (not statistically significant): 67% of primary closure patients readmitted vs 20% of silo patients; bowel obstruction occurred in 17% of primary closure group vs 7% of silo group.
Holland 2010 article 'Gastroschisis: An Update' summarized that there is a need for multi-center prospective studies (due to small numbers at individual centers) and focus on improved evaluation of long-term nutritional and neurodevelopmental outcomes in these relatively well-doing patients.