
Rigid Bronchoscopy for Diagnosis and Treatment of Proximal Pouch Fistula in...
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video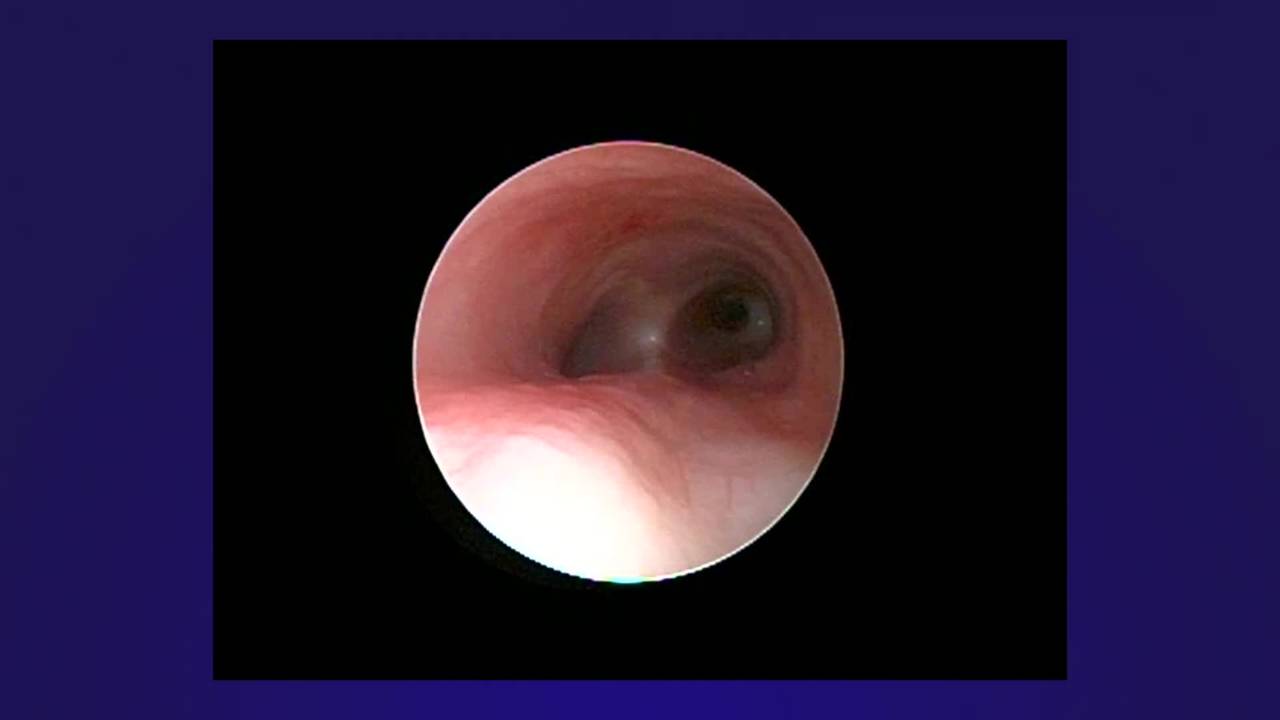
Rigid Bronchoscopy for Diagnosis and Treatment of Proximal Pouch Fistula in...
4 min · Published Feb 2020
Podcast
Case Based Journal Review: Esophageal Atresia in 2022
17 min · Published Aug 2022
Video
Thoracoscopic Repair of Tracheo-esophageal Fistula Tricks: Pediatric Surgery...
19 min · Published Jul 2017
Video
QUAD Conference Commercial
1 min · Published May 2022
Video
Glycopyrrolate for Anastomtic Dehiscence in Esophageal Atresia
2 min · Published May 2017
Video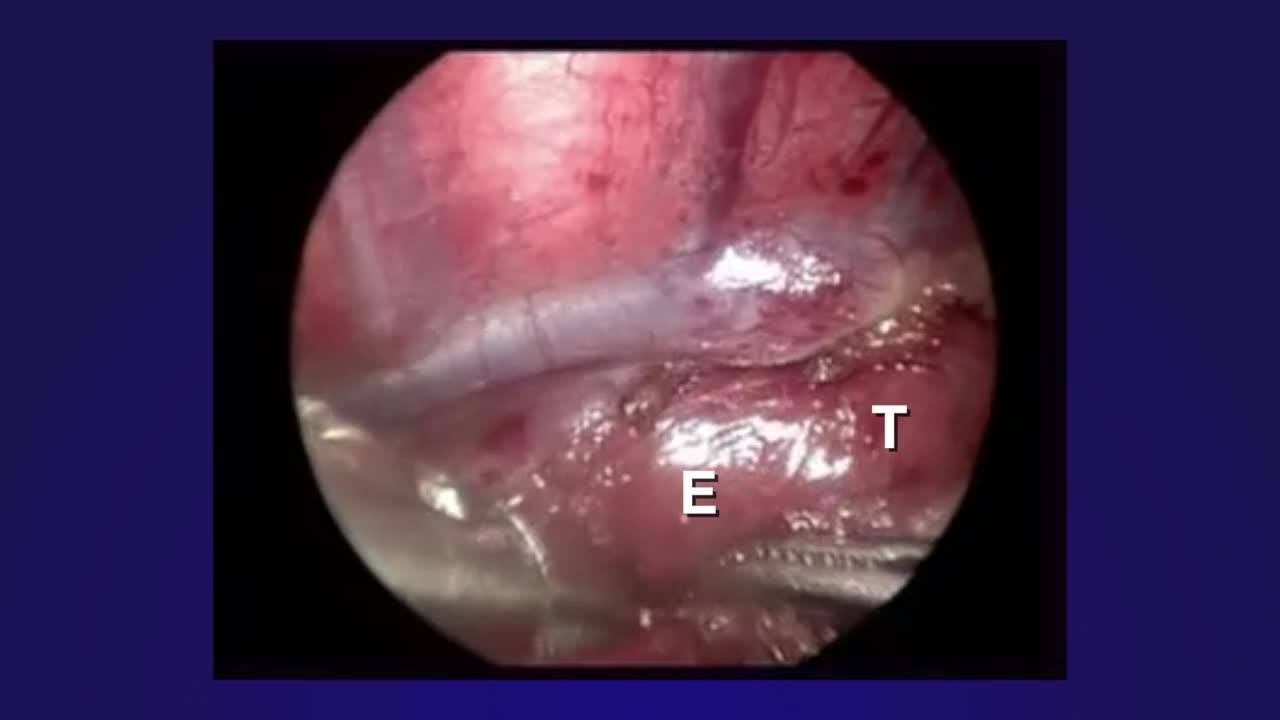
Thoracoscopic Repair of Esophageal Atresia with Distal Tracheo-esophageal...
5 min · Published Feb 2020
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
Proximal fistulas in esophageal atresia can be missed even when rigid bronchoscopy is performed routinely prior to repair of presumed type C esophageal atresia with distal tracheoesophageal fistula.
Proximal tracheoesophageal fistulas are often subtle and look quite different from distal fistulas.
The distal fistula in this case was located 1.5 to 2 centimeters proximal to the carina on initial rigid bronchoscopy.
A routine esophagogram performed 6 days after repair showed a tracheoesophageal fistula despite the absence of a leak or significant stenosis.
Rigid bronchoscopy to evaluate for missed proximal fistula was performed a week after initial repair to minimize the chances of traumatizing the recently ligated fistula.
The proximal fistula appeared as a subtle fold approximately 1 centimeter proximal to the distal fistula site on bronchoscopy.
A thin suction catheter could not be passed through the proximal fistula fold, but a glide wire was easily passed, confirming the presence of a proximal fistula.
Endoscopic treatment involved using a glide wire to stent the fistula open while cauterizing the tract with bugby cautery until the tract and fistula wall were fully cauterized.
Following cauterization, Deflux (dextranomer hyaluronic acid copolymer) was injected into the fistula tract.
The endoscopic procedure was unsuccessful, and the proximal fistula remained patent on esophagogram two weeks later.
The patient subsequently underwent successful repair of the proximal fistula through a right neck incision.
If any suspicion of proximal fistula is seen on rigid bronchoscopy, insufflation of air through the esophageal pouch or installation of methylene blue may help confirm a proximal fistula.