Nothing matches these filters —
clear the search or widen the filters.
Pramod's statements about Posterior Urethral Valves
28 statements
Open the Posterior Urethral Valves collection →
Urologic Fetal Intervention: Cincinnati Fetal Center
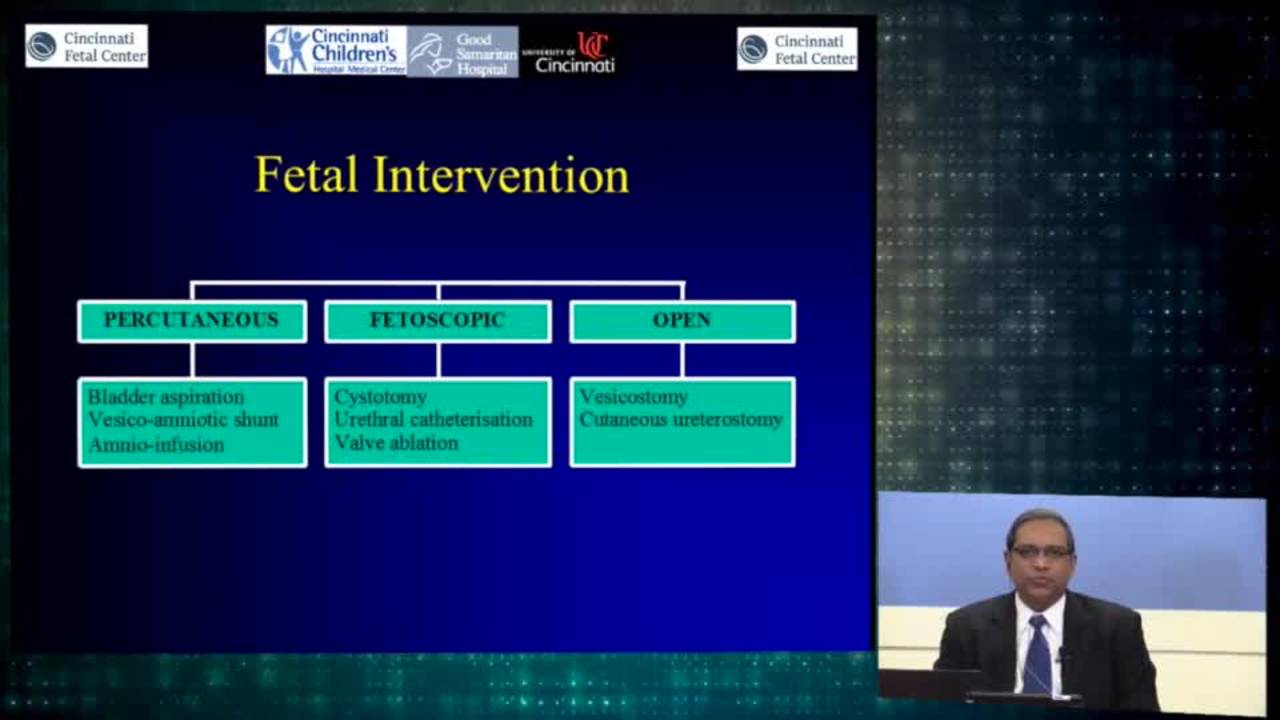 ▶
Ep 2 · 2:04
quote
Not all fetuses with urinary tract obstructions are candidates for interventions.
↗
▶
Ep 2 · 2:04
guideline
Not all fetuses with urinary tract obstruction are candidates for intervention; those too healthy (normal AFI, non-obstructive dilation, unilateral UPJ) or too sick (cystic dysplasia, abnormal karyotype, multiple anomalies) should not be offered fetal surgery.
↗
▶
Ep 2 · 2:33
quote
All of the risk is accountable to the mother.
↗
▶
Ep 2 · 4:00
clinical
Vesicoamniotic shunts have not improved renal outcomes because the long, thin tubes do not adequately reduce bladder pressure; they provide pulmonary survivors but not renal protection.
↗
▶
Ep 2 · 4:49
quote
If the pressure in a bladder exceeds 40 centimeters of water, that does injure the kidneys.
↗
▶
Ep 2 · 4:49
clinical
In adult studies, bladder pressure exceeding 40 cm H₂O (29 mmHg) causes renal injury and abolishes net glomerular filtration.
↗
▶
Ep 2 · 5:13
clinical
Safe bladder pressures for fetal kidneys are unknown; adult thresholds are used by extrapolation.
↗
▶
Ep 2 · 5:13
quote
What are the pressures that are safe in a bladder for a fetus and the fetal kidneys to continue to develop, we don't know.
↗
▶
Ep 2 · 6:53
quote
The shunts have not really provided the improvement in renal function, they have provided us with pulmonary survivors.
↗
▶
Ep 2 · 16:39
clinical
Bladder cycling enabled by fetoscopic valve ablation is physiologically important for bladder health, not for upper-tract protection.
↗
▶
Ep 2 · 17:57
opinion
A urethral fistula from fetoscopic laser ablation can be repaired surgically with minimal morbidity, whereas renal dysplasia cannot be reversed.
↗
▶
Ep 2 · 17:59
quote
I would rather have to deal with a fistula that I can repair surgically than renal dysplasia.
↗
▶
Ep 2 · 18:30
clinical
Posterior urethral valves can sometimes be ablated by blunt mechanical disruption (guidewire and catheter) rather than laser, because the valves are flimsy.
↗
▶
Ep 2 · 18:46
quote
If hydrodistention all by itself could do it, then the amount of pressure developing in the urinary tract should blow open those valves.
↗
▶
Ep 2 · 30:18
clinical
A flexible 4.9 Fr ureteroscope can be introduced through a 10 Fr sheath to improve maneuverability when accessing the fetal bladder neck and posterior urethra.
↗
▶
Ep 2 · 38:44
opinion
Current algorithms reserve the most invasive interventions (open vesicostomy) for the worst-prognosis fetuses, which may be flawed because these patients are least likely to benefit and most likely to suffer maternal and fetal harm.
↗
▶
Ep 2 · 41:06
clinical
Open fetal vesicostomy predisposes the mother to shortened gestation (~10 additional weeks) and very high risk of preterm labor.
↗
▶
Ep 2 · 41:33
epidemiological
Cincinnati performed open fetal vesicostomy in six anhydramniotic fetuses; four died from preterm delivery, one has normal renal function at age 5, and one required transplant.
↗
▶
Ep 2 · 44:27
quote
We struggle with this.
↗
▶
Ep 2 · 44:46
quote
In the one instance where we've got this incredibly successful outcome, I think that that was the right choice for them.
↗
▶
Ep 2 · 47:57
quote
We really need to identify a better marker of renal function, fetal renal function.
↗
▶
Ep 2 · 47:57
opinion
Better biomarkers of fetal renal function are urgently needed to guide intervention selection and predict outcomes.
↗
▶
Ep 2 · 56:35
quote
The creatinine at the time of discharge from the hospital is very misleading.
↗
▶
Ep 2 · 56:52
clinical
Infants with LUTO triple their birth weight in the first year, revealing the true extent of renal reserve; discharge creatinine does not account for this growth.
↗
▶
Ep 2 · 56:52
clinical
Creatinine at hospital discharge is misleading; creatinine at age 1 year is a better predictor of long-term renal function. A creatinine <1.0 mg/dL at age 1 suggests the child will not require renal replacement therapy.
↗
▶
Ep 2 · 57:14
quote
If their creatinine at age one is less than one, most likely that they will not need renal replacement therapy.
↗
▶
Ep 2 · 57:31
quote
The bladder is often underestimated in terms of its importance.
↗
▶
Ep 2 · 57:31
clinical
Polyuria from fetal concentrating defects causes high bladder storage pressures, which damage the upper tracts in a vicious cycle; aggressive postnatal bladder management is required to break this cycle.
↗

