
Thoracoscopic Left Lower Lobectomy for Congenital Pulmonary Airway Malformation
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about congenital pulmonary airway malformation
same diagnosisDive deeper → Congenital Pulmonary Airway Malformation (22 items)Video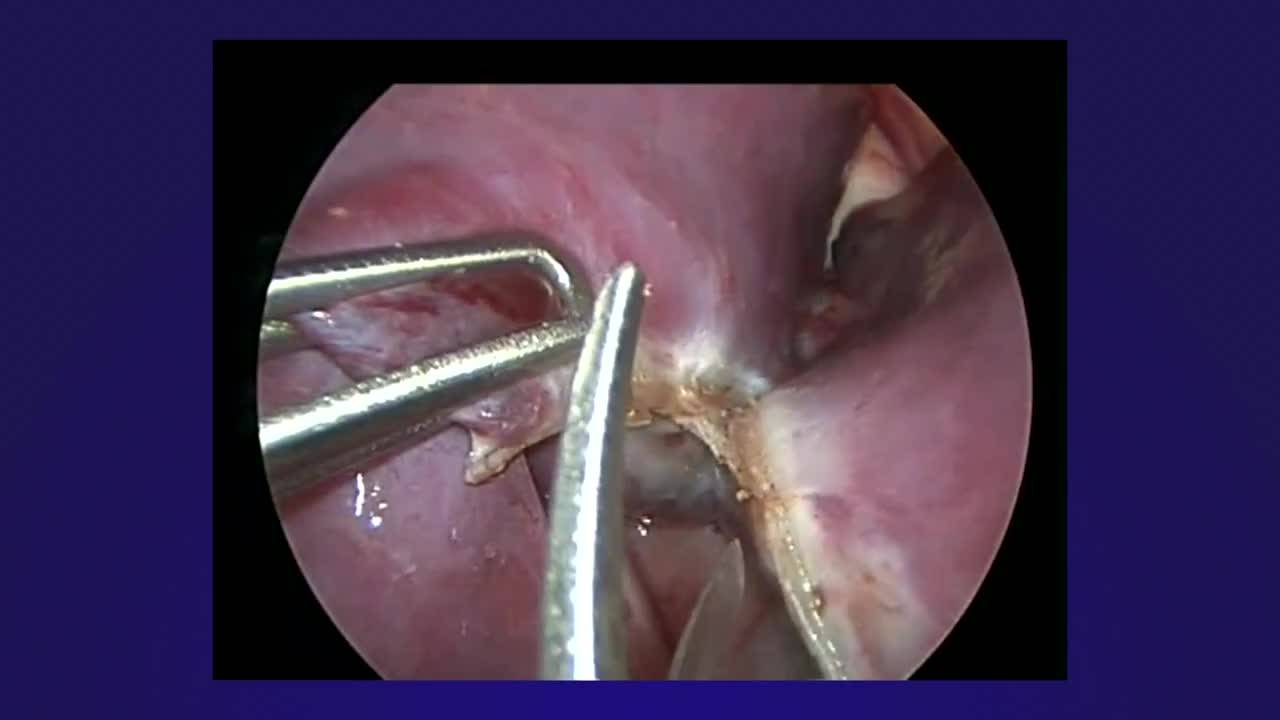
Thoracoscopic Left Lower Lobectomy for Congenital Pulmonary Airway Malformation
9 min · Published Feb 2020
Video
Clinical Symptoms Affect Treatment and Prognosis in Pediatric Patients with Congenital Pulmonary Airway Malformation
55 s · Published Dec 2023
Video
Quick Literature Updates Episode 18
4 min · Published Mar 2025
Podcast
Case Based Journal Review - CPAM in 2022
12 min · Published Apr 2022
Video
Thoracoscopic Upper Lobectomies for Symptomatic Congenital Pulmonary Airway...
5 min · Published Feb 2020
Video
Thoracoscopic Upper Lobectomies for Symptomatic Congenital Pulmonary Airway...
5 min · Published Feb 2020
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
The malformation was a hybrid congenital pulmonary airway malformation diagnosed prenatally.
The patient was asymptomatic at birth and remained asymptomatic through 9 months of age.
CT scan at 4 months showed a left lower lobe CPAM with systemic blood supply arising from the sub-diaphragmatic aorta.
The operation was performed at 9 months of age.
The left lung is isolated by right main stem intubation.
The patient is placed in the right lateral decubitus position with surgeon and assistant operating facing the patient.
A large arterial vessel coming through the diaphragm medial to the inferior pulmonary ligament and entering the left lower lobe confirms a hybrid lesion.
The inferior pulmonary ligament is divided all the way to the border of the inferior pulmonary vein to mobilize the left lower lobe off the diaphragm.
Division of the inferior pulmonary ligament allows stretching of the systemic arterial vessel for skeletonization with hook cautery.
The systemic arterial vessel is double-clipped proximally and divided distally with a ligature device.
The approach of proximal clipping and distal ligature division is used repeatedly for control of several major vessels.
The fissure is completed using ligature and sharp dissection.
Division of pulmonary parenchyma in the fissure allows visualization of pulmonary artery branches to the lower lobe.
The dissection should be kept as bloodless as possible, with any bleeding from divided parenchyma controlled early with ligature.
Excellent visualization is essential for adequate vascular control.
A right angle dissector is extremely useful in skeletonizing vessels and gaining adequate distance for safe ligation.
Dissection in the fissure always proceeds from medial to lateral.
While ligature can be used as the sole method of vessel control, the surgeon prefers to apply clips proximally if adequate vessel length has been achieved.
Once the pulmonary artery and all pulmonary parenchyma in the fissure is divided, the bronchus comes into view.
The inferior pulmonary vein is skeletonized using a right angle dissector.
The junction of the inferior pulmonary vein and the left atrium can be clearly seen after adequate dissection.
It is quite common for the inferior pulmonary vein to consist of two major tributaries that join as they approach the left atrium, in addition to one or more small tributaries.
When the inferior pulmonary vein has two major tributaries, it is best to dissect each tributary separately.
Each pulmonary vein tributary is controlled by clipping on the cardiac side and applying ligature on the pulmonary side.
Hook cautery is used to clean the bronchus of surrounding lymphatic and adventitial tissue.
An endo-GIA device is introduced directly through the chest wall and used to staple and divide the bronchus.
The specimen is extracted by slightly enlarging the posteriormost port site.
A chest tube is placed at the end of the operation.
The patient was extubated at the end of the procedure.
The patient was discharged on the 2nd postoperative day with excellent recovery.
Chest X-ray 2 years after the procedure showed good result.