


From
StayCurrentMD
Update Course Rewind: Updates in Indocyanine Green (ICG) 2023
With Dr. Seth Goldstein · hosted by Dr. Cecilia Gigena
Chapter 1 of 4 · Case-Based Learning
ICG introduction
Introduction to ICG and Sentinel Node Case Presentation
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about this diagnosis
Alveolar rhabdomyosarcomaVideo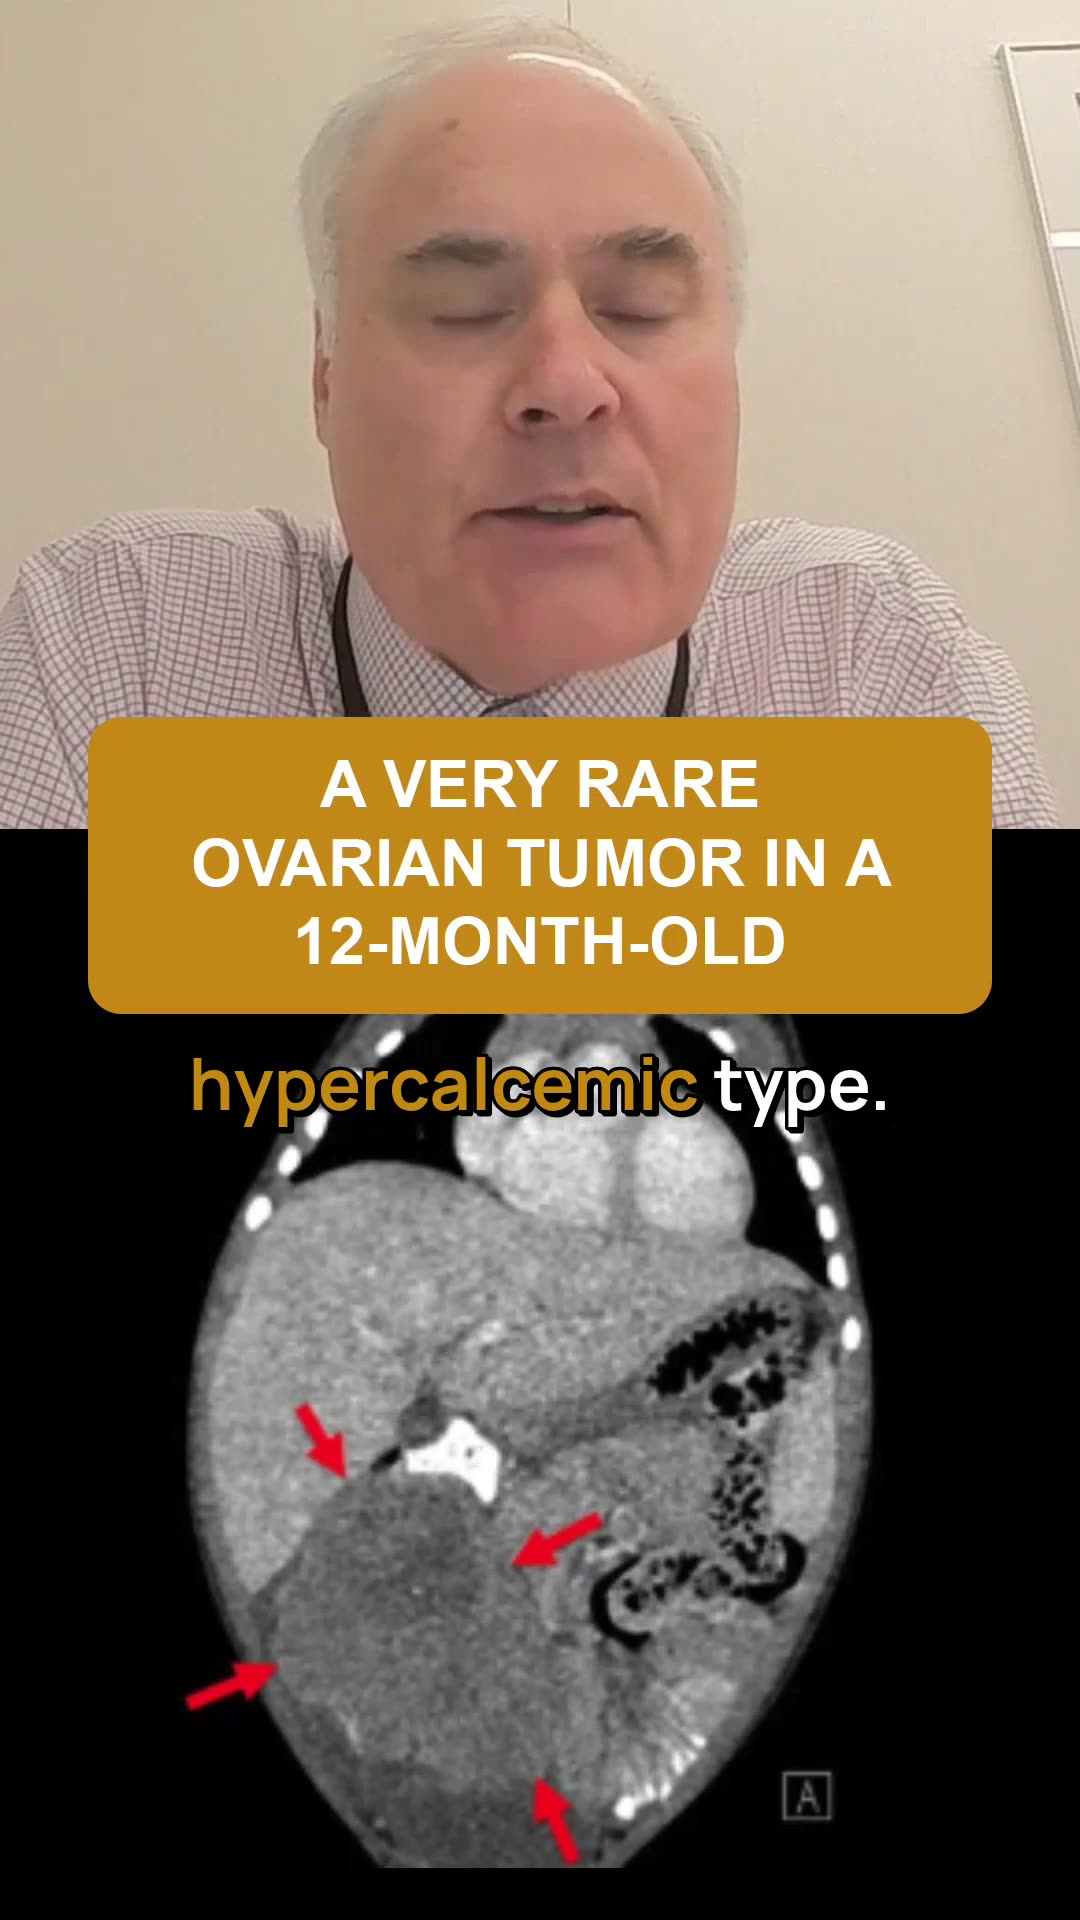
Rare Ovarian Tumor in Infants: Small Cell Carcinoma of Ovary, Hypercalcemic Type & SMARCA4 Mutation
21 s · Published Oct 2026
Video
Can Normal X-Rays Miss Metastatic Neuroblastoma? A Pediatric Radiology Case Study
26 s · Published Oct 2026
Video
Can Fractures Be a Sign of Hepatoblastoma in Children? Understanding Pediatric Liver Cancer Symptoms
37 s · Published Oct 2026
Video
Pancreas, Muscle, and Subcutaneous Fat Atrophy in Patients Undergoing Radiation for Neuroblastoma
47 s · Published Oct 2026
Podcast
Hepatoblastoma
Todd Ponsky · 54 min · Published Oct 2026
Podcast
Wilms Tumor
Todd Ponsky · 64 min · Published Oct 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
Indocyanine Green was discovered by the post-World War II Kodak company and has been FDA approved since the 1960s.
ICG is a safe, harmless fluorescent contrast that can be injected subcutaneously or intravenously depending on the use.
ICG usage has really developed in hepatobiliary surgery.
Sentinel node biopsy at the time of port placement for alveolar rhabdomyosarcoma is pretty much standard of care.
Pediatric surgeons can consider use of ICG as an adjunct to sentinel node identification.
ICG can be used in the operating room with equipment that is either already present or about to be standard in all laparoscopic towers.
After indocyanine injection into the tumor, ICG travels to the sentinel node over the course of 45, 60, or 75 seconds.
ICG is exclusively biliary cleared.
For detecting liver tissue metastases in the chest, ICG should be given the day before surgery so it is the only thing left in the chest by the time of thoracotomy.
At the time of thoracotomies for lung metastases, if ICG is given the day before, additional metastases can be found beyond what is detected by palpation and visual inspection.
Spots detected by ICG in the chest after preoperative administration are also positive on histology.
Fluorescent ureteral stents that emit infrared light can be detected by standard laparoscopic systems and help protect ureters during pelvic tumor resection.
Fluorescent ureteral stents can enable minimally invasive approaches to cases that would otherwise require open surgery due to ureteral proximity to tumor.
Technetium-99 radio tracer is normally used for sentinel node location and can be detected with a special detector.
Using radio tracer requires coordination between oncologists and surgeons to purchase machines and coordinate tracer injection with same-day operations.
Most new laparoscopic towers have an integrated system with a specific mode that can detect ICG.
ICG is being used as the primary localizer of the sentinel node while still confirming with Technetium.
For liver transplant due to hepatic carcinomas, zero metastasis is required, which often necessitates bilateral lung metastasectomies.
ICG is excreted by the biliary tract.
ICG can be used to detect sentinel nodes in many types of cancer using either laparoscopic or open instruments.
Given 24 hours in advance, ICG can be useful to detect hepatocarcinoma lung metastasis because it is primarily excreted through hepatic cells.