
Technique: Laparoscopic Repair of Duodenal Atresia, Ladd's Procedure, and...
With Dr. Steve Rothenberg · StayCurrentMD
Part of
Malrotation 7 items
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about duodenal atresia
same diagnosisVideo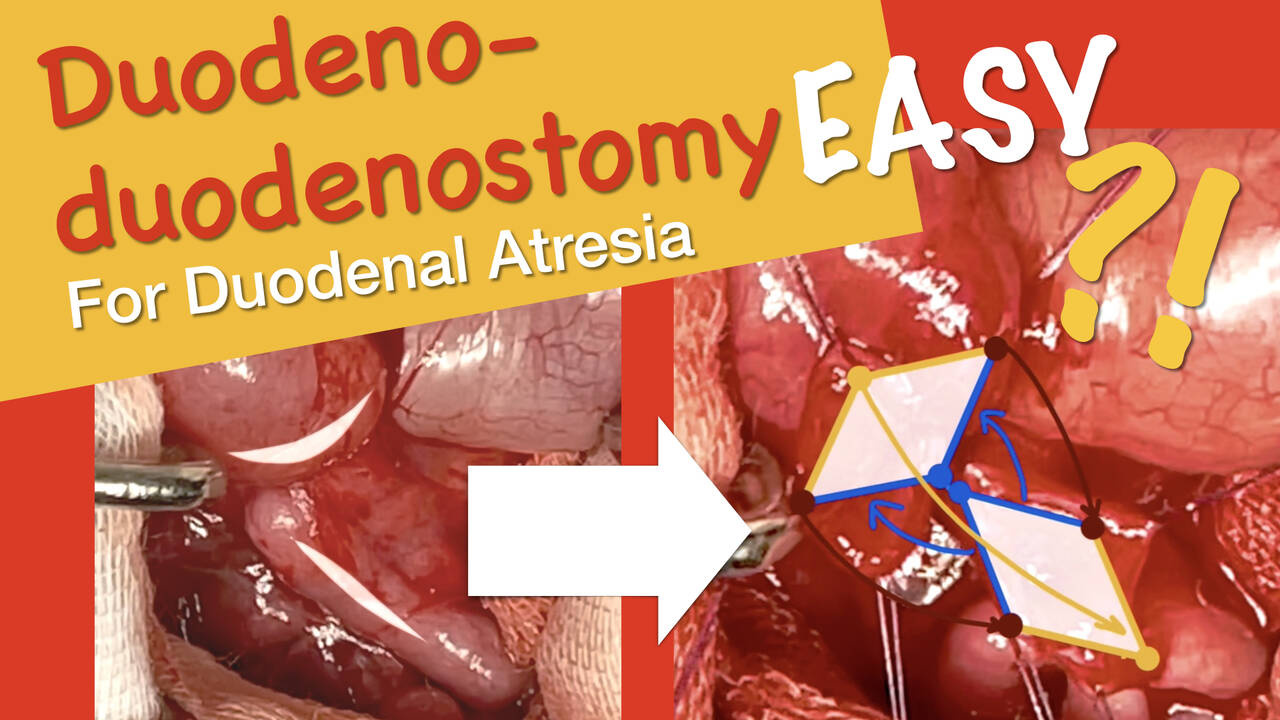
Duodeno-duodenostomy for Duodenal Atresia
7 min · Published Jun 2021
Podcast
Intestinal Rehabilitation, Episode 2: Overwhelming intestinal damage, Part 1
13 min · Published Feb 2022
Video
Enhanced Recovery After Surgery (ERAS) Program: Update Course 2016
44 min · Published Jul 2017
Video
7th Annual Pediatric Surgery Update Course 2019 - FULL SHOW
285 min · Published Jul 2020
Podcast
Tracheoesophageal Fistula with Dr. Daniel von Allmen
45 min · Published Dec 2016
Video
Tracheoesophageal Fistula with Dr. Daniel von Allmen
Dr. Todd Ponsky · 45 min · Published Dec 2016
Only a few other public items share this expert — go deeper there →
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
The patient is a 1 day old infant who had a prenatal diagnosis of duodenal atresia
Port placements consist of a 4 millimeter scope in the umbilicus, a 3 millimeter port in the left mid quadrant, and a 3 millimeter stab wound in the right mid quadrant, triangulated towards the right upper quadrant
The 3 millimeter sealer is an excellent dissecting device and can be used in safe energy in close approximation to both the gallbladder and the small bowel
A transabdominal stitch using a 30 Prolene on an RB1 needle is placed through the anterior abdominal wall in the right upper quadrant to retract the gallbladder superiorly
The child is malrotated with a complete duodenal atresia
The bowel is run from proximal to distally to ensure that there are no further Ladd's bands and to completely de-rotate the bowel
A Meckel's diverticulum is found in the distal ileum during the procedure
All of the small bowel is placed on the patient's right and the large bowel on the patient's left
Widening the mesenteric base should diminish the chance of volvulus in the future
A transverse enterotomy is made at the most dependent portion of the dilated proximal segment
The enterotomy in the distal segment is longitudinal
There is increased smoke and debris from using electrocautery compared to the 3 millimeter sealer
A transabdominal stitch aligns the two sides of the bowel to perform the side to side anastomosis
A pre-cut Vicryl suture approximately 10 to 12 centimeters in length is used to run the back row of the anastomosis
In some cases, the distal duodenal segment is more fixed to the retroperitoneum, making this part of the procedure more difficult, but the same technique is used with excellent result
The surgeon prefers running suture over interrupted suture as it works extremely well and is more efficient
The entire procedure took approximately 50 minutes
Approximately 10% of patients undergoing laparoscopic repair of duodenal atresia have malrotation
The patient is a 2.8 kg child
A nasogastric tube is left to suction for approximately 3 to 4 days, and in most cases feeds are started by the 5th day
This child started eating on the 5th postoperative day and was on full feeds by the 8th postoperative day
The base of the Meckel's diverticulum could adequately be divided without compromising the lumen of the bowel, so a decision was made to remove it using the 5 millimeter stapler
The left quadrant 3 millimeter port was changed to a 5 millimeter port to allow insertion of the endoscopic stapler
Because of the malrotation, the appendix was also removed
The child was discharged to home on the 10th postoperative day