
Hepatoblastoma: Update Course 2014
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video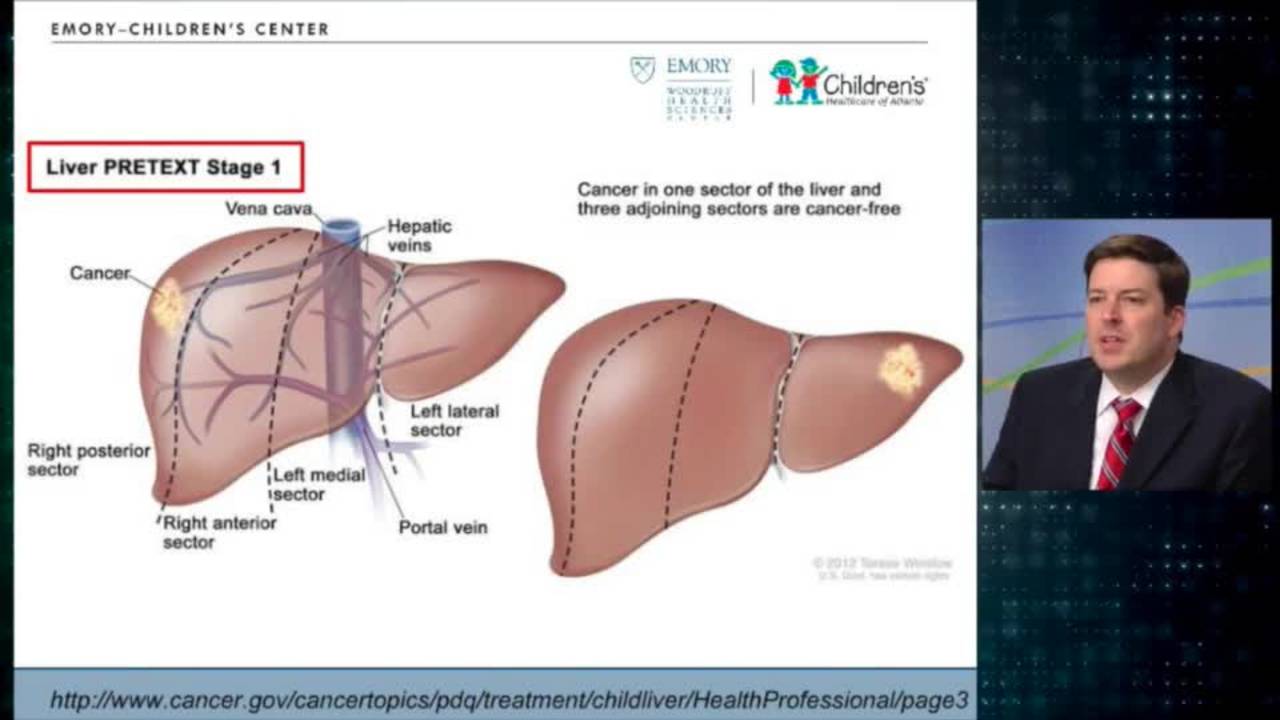
Hepatoblastoma: Update Course 2014
Published Jul 2017
Video
Hepatoblastoma with Dr. Greg Tiao
CCHMC Pediatric Surgery · Published Mar 2022
Video
Quality of Life Outcomes for Patients Who Underwent Conventional Resection and Liver Transplantation for Locally Advanced Hepatoblastoma
1 min · Published Jan 2026
Video
BOB Ped Surg 2023 - Andrew Fleming, AAP - Presentation
Published Feb 2023
Podcast
Hepatoblastoma with Dr. Greg Tiao
10 min · Published Feb 2022
Video
Retreatment with Cisplatin May Provide a Survival Advantage for Children with Relapsed/Refractory Hepatoblastoma: An Institutional Experience
1 min · Published Jan 2026
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
PRETEXT staging stands for pre-treatment extent of disease and is based on segmental liver anatomy, performed prior to chemotherapy.
PRETEXT staging has a tendency to overstage because it is based purely on imaging, and bulky tumors make it difficult to assess true vascular invasion versus mass effect.
POSTTEXT staging refers to extent of disease after neoadjuvant chemotherapy has been given.
Key staging annotations include involvement of the retrohepatic cava or hepatic veins, and the portal vein bifurcation.
COG recommendations state that PRETEXT I-II tumors with clear 1 cm margins and no vascular involvement can be resected locally without referral to specialized centers.
Most tumor volume shrinkage from chemotherapy occurs within the first two cycles.
After 2 cycles of chemotherapy, if the tumor has not shrunk to a resectable size, the patient should be evaluated for transplant.
As hepatoblastoma tumors shrink with chemotherapy, they do not shrink away from vascular supply significantly; size decreases but vascular margins do not substantially improve.
Survival after extensive or 'heroic' resections (tumor liver explants with back table resections and reimplants, portal vein reconstructions, hepatic vein reconstructions) is not as good as transplant survival.
There has been a move away from heroic resections in hepatoblastoma due to inferior survival compared to transplantation.
Patients who undergo rescue transplant after failed resection do far worse than patients who have a planned transplant upfront.
Current thinking is to refer patients to a transplant center early, even if two cycles of chemotherapy will be given first, to have pre-transplant evaluation completed and the patient integrated into the system.
Primary transplant patients do surprisingly well despite immunosuppression for cancer, particularly in liver tumors.
In the UK, all biliary atresia patients are referred upfront to a transplant center.
For non-transplant center surgeons performing hepatoblastoma resection, there must be 95% confidence of successful resection with adequate margins before proceeding; otherwise referral to a transplant center is indicated.
Anatomic resection with a good margin is appropriate for local management; disease near hepatic veins, crossing the liver, or involving the portal vein should be referred.
Liver transplant surgeons have extensive experience operating on the liver, which may benefit pediatric surgeons managing borderline-resectable hepatoblastoma cases.
Despite advanced imaging, the truth about resectability is determined at the time of operation.
In Europe, all liver tumors receive chemotherapy upfront before surgery to make the tumor smaller and potentially avoid transplantation.
Trisegmentectomy for cure is a reasonable approach to avoid lifelong immunosuppression from transplantation.
Central hepatectomies have been performed successfully for hepatoblastoma cure without requiring transplant, though it is a difficult operation.
For core needle biopsy of hepatoblastoma, approximately 10 passes are recommended, going through an area that includes normal parenchyma and tumor.
There are two camps regarding pulmonary metastases in hepatoblastoma: one advocates resecting metastases upfront before hepatectomy; the other suggests waiting until after hepatectomy because liver regeneration growth factors may stimulate previously unrecognized lung sites.
There is no good data on either side of the pulmonary metastases timing debate; all evidence is limited to a handful of patients.
Papers examining stage 4 hepatoblastoma with pulmonary metastases are limited to cohorts of less than 20 patients, making it difficult to draw good conclusions.
There may be reporting bias in hepatoblastoma transplant literature: successful cases (good chemo response, transplant, long-term survival) are reported, but failures may not be.
PLUTO (Pediatric Liver Unresectable Tumor Observatory) is an international group seeking to answer questions about unresectable hepatoblastoma that cannot be answered at individual or multi-center level within North America or Europe.
It will likely take several years before PLUTO can answer key questions about unresectable hepatoblastoma management.