
Congenital Cystic Lung Lesions: Update Course 2014
With Dr. Steve Rothenberg · hosted by Dr. Todd Ponsky · StayCurrentMD
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about congenital cystic lung lesions
same diagnosisOnly a few other public items share this diagnosis — nothing to add yet.
Video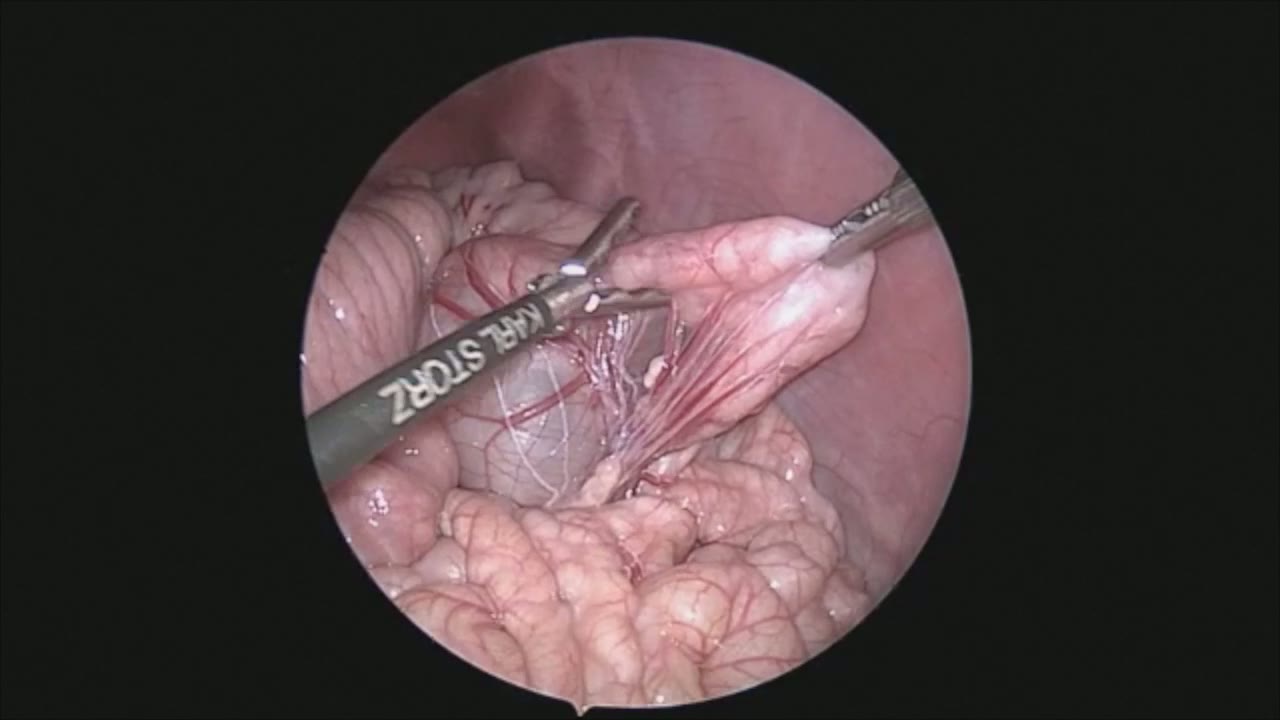
sealer demo
Dr. Steve Rothenberg · 3 min · Published May 2026
Video
pyloric knife
Dr. Steve Rothenberg · Published May 2026
Video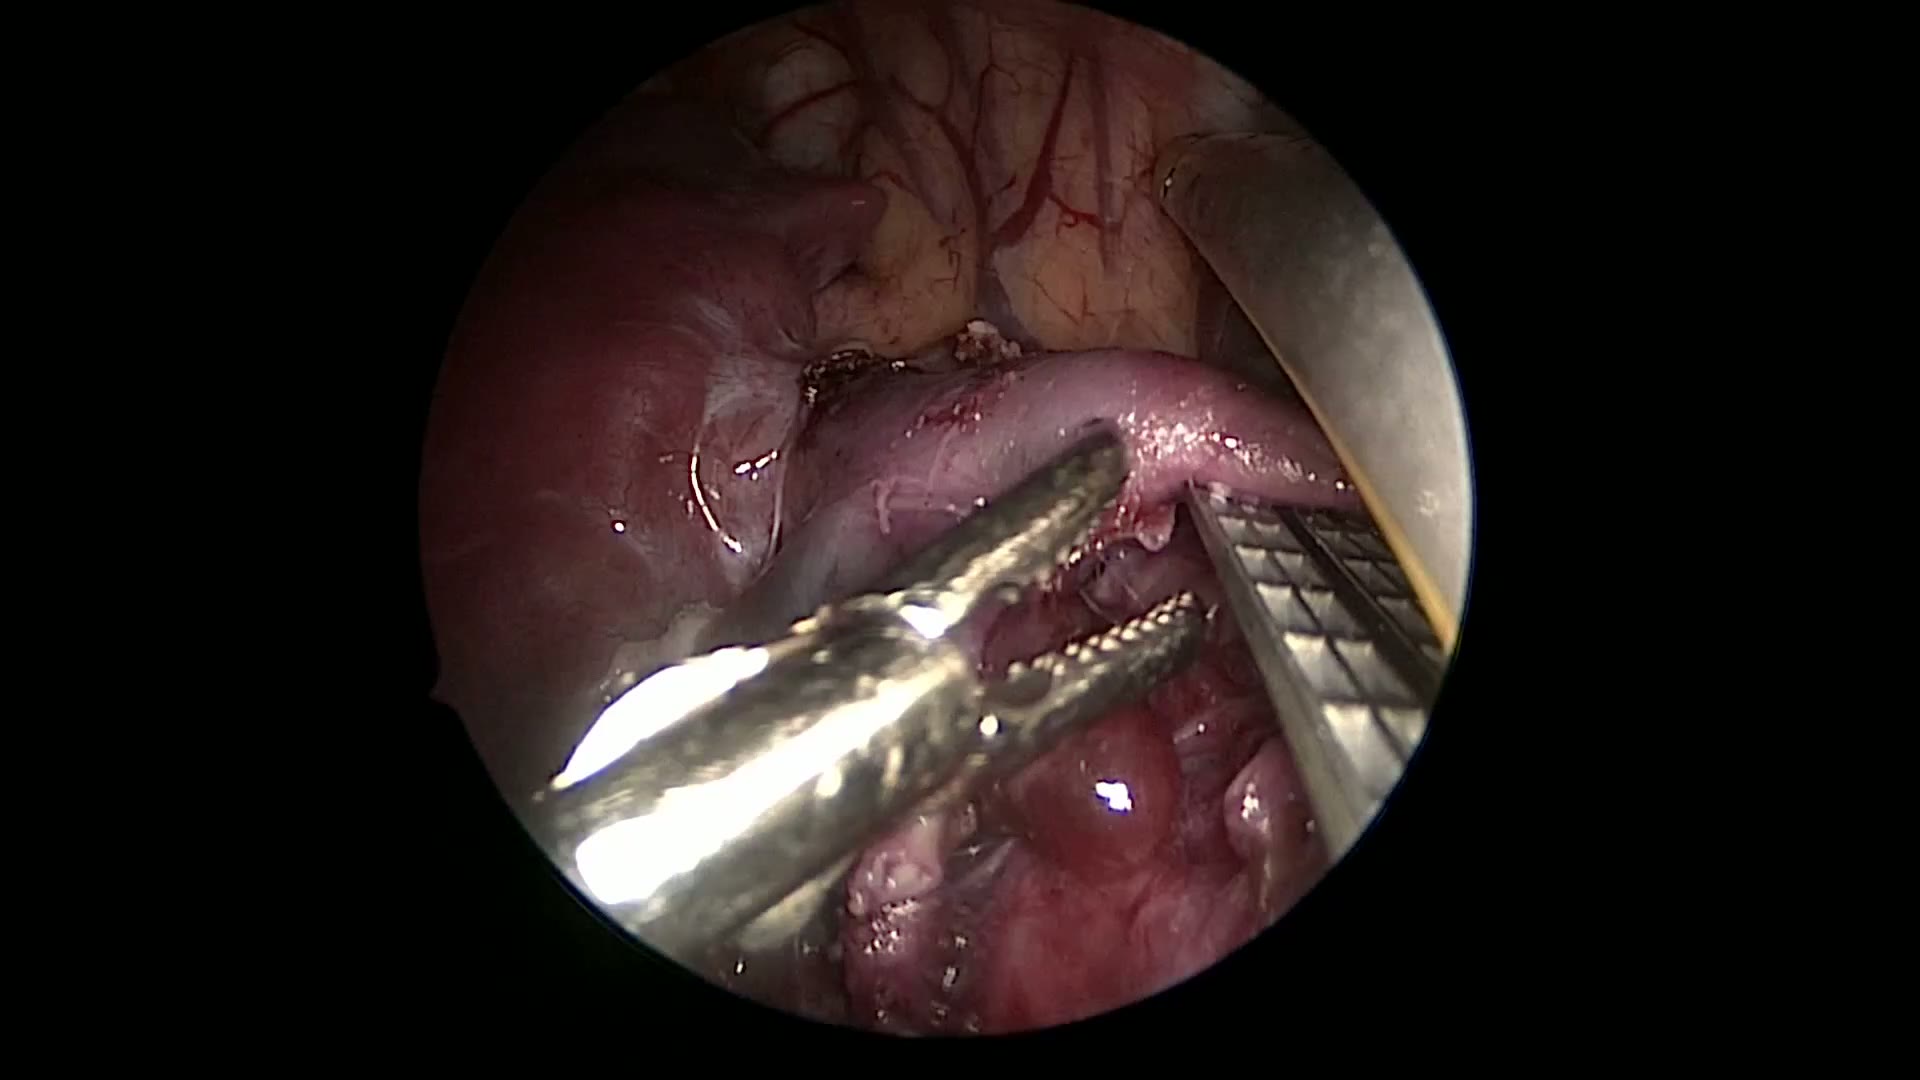
pulm artery LLL
Dr. Steve Rothenberg · 9 s · Published May 2026
Video
plication narrated
Dr. Steve Rothenberg · 6 min · Published May 2026
Video
percuvance redo nissen
Dr. Steve Rothenberg · 5 min · Published May 2026
Video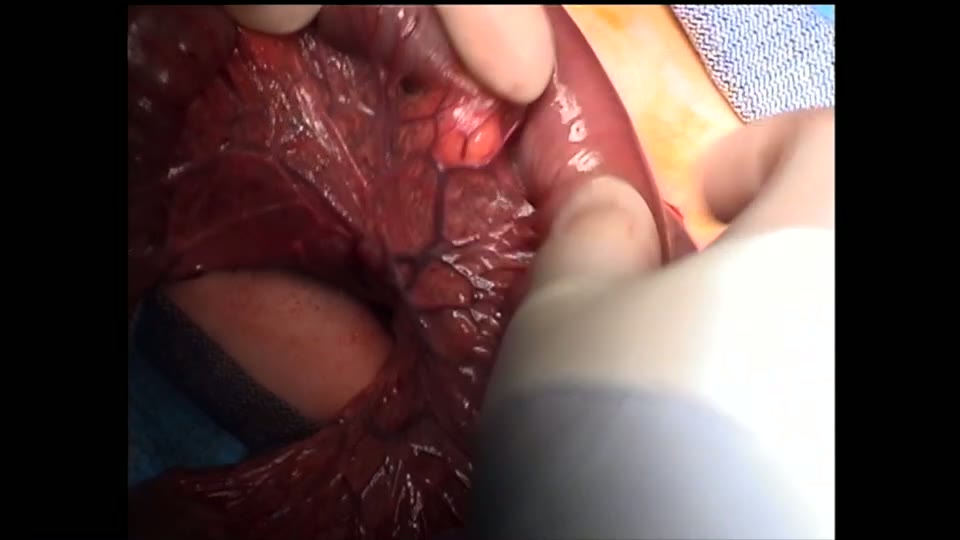
open bowel anast
Dr. Steve Rothenberg · Published May 2026
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
Fetal MRI for congenital cystic lung lesions does not change management in most cases unless the fetus shows signs of hydrops or the center uses prenatal steroids.
Prenatal steroids are indicated for microcystic lesions with CVR (congenital pulmonary airway malformation volume ratio) >1.6, based on UCSF findings that steroids can reduce lesion size or prevent growth relative to fetal growth.
Prenatal steroids do not work on macrocystic lesions, only microcystic lesions.
CT scan can identify multifocal disease in congenital cystic lung lesions, which may change surgical management (e.g., disease in all three lobes of one lung).
Approximately 3 patients in several hundred cases had bilateral congenital cystic lung disease, requiring altered management.
Operative time and complication rate are lower when congenital cystic lung lesions are resected earlier (3 months) compared to later (9+ months), supported by published data.
Asymptomatic infants with congenital cystic lung lesions develop subclinical inflammation and infection between 3 and 9 months of age, manifesting as enlarged lymph nodes and fissure inflammation that complicate surgery.
A 3mm vessel sealer can safely seal and divide vessels up to 5mm in diameter during pediatric thoracoscopic surgery.
Even in asymptomatic infants who have never had a cold or chest infection, significant inflammation can develop in congenital cystic lung lesions by 1 year of age, making surgery more difficult.
At 3 months of age, thoracoscopic lobectomy in a 5kg infant provides adequate working space with 3mm instruments; space is not a limiting factor.
The Netherlands takes a more conservative approach to congenital cystic lung lesions compared to Germany.
In Germany, the standard practice is to operate on any cystic lung lesion at 3-6 months of age because of potential malignancy risk later in life.
Anatomic segmental resection is key when performing limited resection for congenital cystic lung lesions; non-anatomic resection carries risk of recurrent cystic disease.
One child who underwent segmental resection for CPAM has shown evidence of recurrent cystic disease on follow-up.
In a personal series of over 300 lobectomies for cystic lung disease, the malignancy rate was 1-2%, including 2 pulmonary blastomas and 1 adenocarcinoma.
Neoplastic mucinogenic proliferations in CPAM may be associated with KRAS mutation, which is also a marker in adult small cell carcinoma and colon cancer.
Columbia pathology review identified 4 additional cases of CPAM with neoplastic mucinogenic proliferations, a finding not previously reported in the literature.
30-40% of children with congenital cystic lung disease will have a significant pulmonary infection at some point during their life.
Once congenital cystic lung lesions become infected, they are much more difficult to resect surgically.
All thoracoscopic lobectomies for congenital cystic lung lesions should be performed thoracoscopically at centers with expertise; if a center cannot perform the procedure thoracoscopically, referral should be considered to avoid thoracotomy morbidity.
Long-term pulmonary function studies are needed to document that infants who undergo lobectomy compensate with growth of remaining lung tissue and do not have significant disability.
Morsellating tumor-containing lung tissue during specimen extraction does not upstage the tumor or change treatment according to hematology-oncology consultation, though patients require surveillance.
All three malignancies (2 blastomas, 1 adenocarcinoma) in the surgeon's series occurred in children under 1 year of age.