


From
StayCurrentMD
Technique: Laparoscopic Assisted Pull-through for Hirschsprung's Disease
With Dr. Steve Rothenberg
Chapter 1 of 6 · Surgical Management
Setup & biopsy
Patient positioning, port placement, and biopsy
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Podcast
The Colorectal Quiz Episode 4
Marc Levitt · 19 min · Published Feb 2021
Video
Surgical treatment for Hirschsprung’s Disease: An ERNICA animation for parents and families
3 min · Published Dec 2023
Video
Quick Literature Updates Ep 23
4 min · Published Oct 2025
Video
Transitional Care in Anorectal Malformation and Hirschsprung's Disease
1 min · Published Jul 2024
Video
Transition From Pediatric to Adult Healthcare for Colorectal Conditions: A Systematic Review
58 s · Published Sep 2024
Video
Transition of Care - A general overview by Silja Kosolove
21 min · Published Nov 2023
Video
Validation of an anorectal malformation trainer - Can a high-fidelity model simulate real life?
1 min · Published Jun 2026
Video
Complications and Long-Term Outcomes of Patients With Cloacal Malformation After Bowel Neovagina...
1 min · Published Jun 2026
Video
Safety and utility of long-acting steroid injection for management of post-operative stricture...
1 min · Published Jun 2026
Video
Association Between Social Determinants of Health and Choice of Urinary Reconstruction in Children
1 min · Published Jun 2026
Video
The Perineal Body Preserving PSARP (PPP)
11 min · Published Jun 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video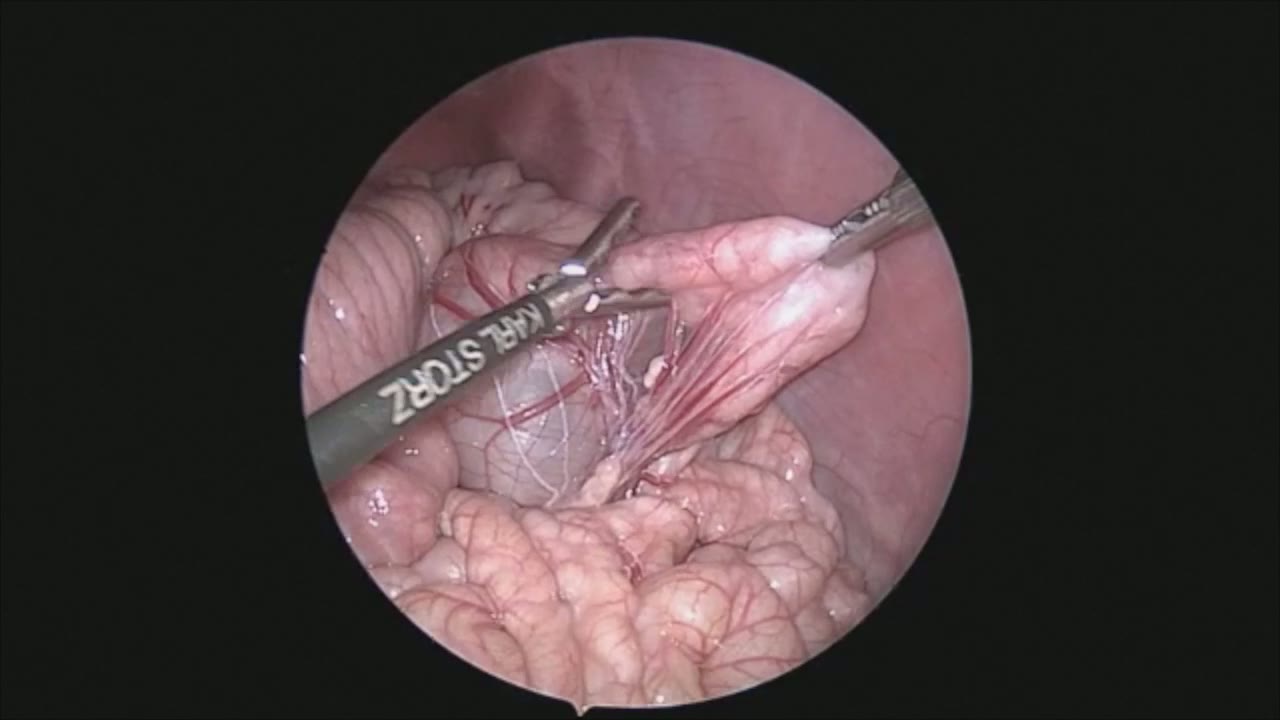
sealer demo
Dr. Steve Rothenberg · 3 min · Published May 2026
Video
pyloric knife
Dr. Steve Rothenberg · Published May 2026
Video
pulm artery LLL
Dr. Steve Rothenberg · 9 s · Published May 2026
Video
plication narrated
Dr. Steve Rothenberg · 6 min · Published May 2026
Video
percuvance redo nissen
Dr. Steve Rothenberg · 5 min · Published May 2026
Video
open bowel anast
Dr. Steve Rothenberg · Published May 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
The key to mesenteric dissection is staying exactly adjacent to the colon wall to prevent injury to surrounding structures.
Because all heat and energy remains between the jaws of the sealer, there is no danger in injuring surrounding structures by brushing aside them with the sealer.
Small perforating vessels are grasped, sealed, and pulled down off the rectal wall circumferentially to dissect along the aganglionic portion of the colon.
The advantage of the 3-millimeter sealer is that it can both dissect off vessels and dissect around the colon to mobilize tissue, with no risk of pass-pointing as with a 3-millimeter hook.
There is no need to perform instrument changes with the right hand throughout the case; a bowel grasper is in the left hand and the sealer is the only instrument used in the right hand.
Carrying the dissection down to the pelvic floor limits the amount of transanal dissection necessary and decreases the risk of injury to the external sphincter.
Because there is no energy spread from the tips of the instrument, it is safe for the instrument to be adjacent to the bladder, vagina, prostate, and other surrounding structures.
Energy only between the jaws of the instrument diminishes the risk of injury to the ureters and other vital structures such as the vas deferens.
When diagnosed, the preference is to perform this operation in the newborn period prior to discharge to home, as the operation is extremely safe with current technology.
It is acceptable if the child tolerates rectal irrigations to let them grow before surgery.
A series of traction stitches are placed inside the anus just proximal to the dentate line and then out to the skin, slightly inverting the anus so the dentate line can be clearly visualized; 4 to 8 sutures are used.
A mucosal incision is made with handheld cautery 2 to 3 millimeters proximal to the dentate line.
Traction or stay sutures are placed in the mucosa to help retract it and allow for submucosal dissection.
The key to the transanal portion is that it should all take place externally to the anus, with no retractors ever placed within the external sphincter, which may cause these muscles to be damaged.
The beauty of the laparoscopic dissection down to the pelvic floor is that it allows release of the area so dissection can be carried out outside of the anus, protecting the external sphincter muscles and improving the chance of good continence.
Sharp dissection is preferred to mobilize the submucosal space, although blunt dissection can also be used.
The dissection is carried around circumferentially until the muscular cuff everts, at which point the peritoneal cavity is entered.
A stitch is placed as a retractor so the muscular cuff can be divided at the 6 o'clock position, and the dissection is carried circumferentially, allowing the colon to be pulled down through the anus.
The biopsy site is 5 to 6 centimeters above the obvious transition zone.
Remaining mesenteric attachments are taken externally using the 3-millimeter sealer to allow mobilization 5 to 6 centimeters above the biopsy site.
Laparoscopy is used to ensure proper orientation of the pull-through and that no structures are caught under the mesentery.
The colon is divided 5 to 6 centimeters above the biopsy site, which is 5 centimeters above the obvious transition zone.
Four quadrant stay sutures are placed, and 3 to 4 additional sutures are placed in each quadrant for a total of 12 to 16 sutures forming the new coloanal anastomosis, using 4-0 Vicryl suture in newborns.
This operation took 70 minutes.
The child was left without a nasogastric tube and started stooling the morning following surgery.
The patient was started on feeds less than 24 hours after the procedure.
The anastomosis is calibrated with a number 12 Hegar dilator at the end of the procedure.
A gauze packing is placed in the anus at the end of the procedure.
The 3-millimeter sealer is used as the primary mode of dissection for laparoscopic-assisted pull-through in Hirschsprung's disease.
The patient is a newborn weighing 3.2 kg.
A supraumbilical ring incision is used for the Veress needle and 4-millimeter trocar camera port in small newborns, with the trocar placed just to the left of midline to avoid the umbilical vein.
A full-thickness biopsy is obtained from the muscular wall approximately 5 centimeters above the transition zone between the distal sigmoid and rectum.