
Esophageal Atresia & Tracheoesophageal Fistula (EA/TEF) Types Explained for Pediatric Surgery
hosted by Dr. Jill Knerath
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
QUAD Conference Commercial
1 min · Published May 2022
Video
Glycopyrrolate for Anastomtic Dehiscence in Esophageal Atresia
2 min · Published May 2017
Video
Thoracoscopic Repair of Tracheo-esophageal Fistula Tricks: Pediatric Surgery...
19 min · Published Jul 2017
Podcast
Journal of Pediatric Surgery Article Review: December 2021
16 min · Published Jan 2022
Video
Rigid Bronchoscopy for Diagnosis and Treatment of Proximal Pouch Fistula in...
4 min · Published Feb 2020
Video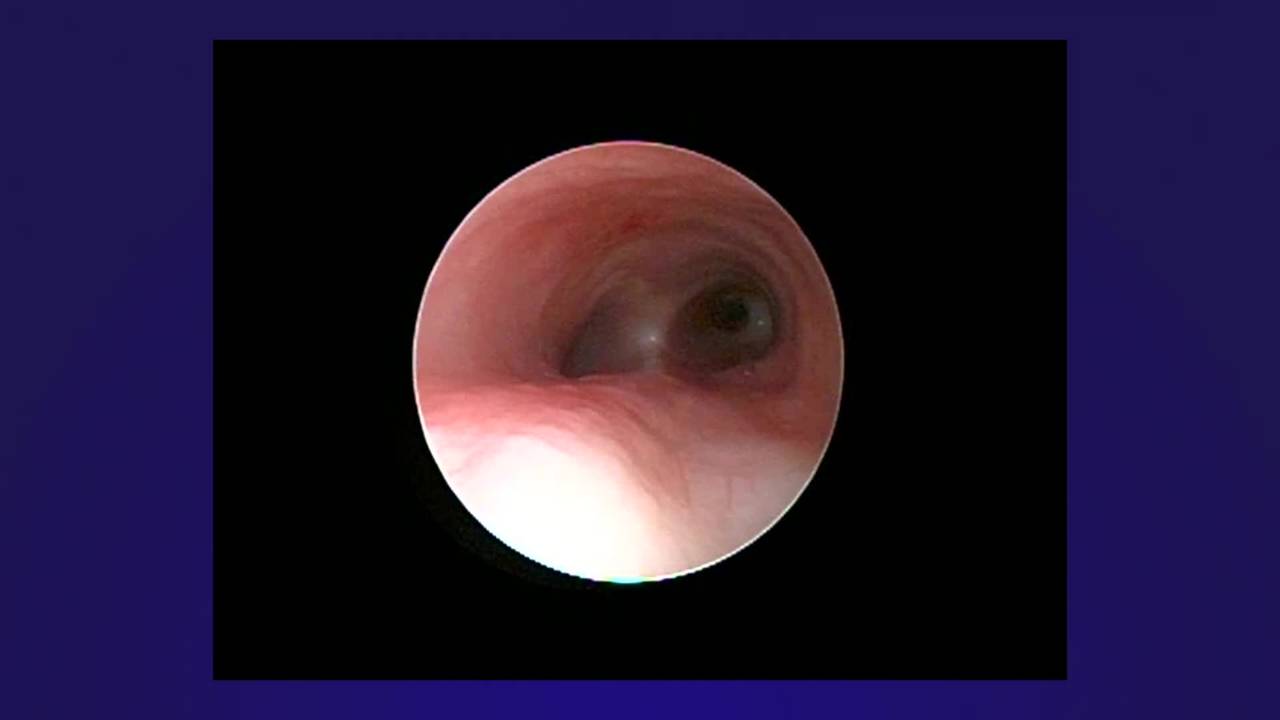
Rigid Bronchoscopy for Diagnosis and Treatment of Proximal Pouch Fistula in...
4 min · Published Feb 2020
What the experts said
EA/TEF is a basic concept in pediatric surgery.
In normal anatomy, the esophagus goes straight down to the stomach with no atresia or interruptions, and the trachea goes straight down to the lungs with no connections between the two.
Type A EA/TEF consists of esophageal atresia proximally and distally in the esophagus, preventing solids and liquids from reaching the stomach, with no connection between esophagus and trachea.
Type B EA/TEF has distal esophageal atresia and a proximal fistula, allowing solids and liquids to enter the trachea while the stomach remains empty.
Type C EA/TEF is the most common type.
Type C EA/TEF has proximal esophageal atresia and a distal fistula, allowing air to reach both lungs and stomach while solids and liquids cannot reach the stomach.
Type D EA/TEF has both a distal fistula and a proximal fistula, allowing solids and liquids into the trachea and air into both lungs and stomach.
Type E EA/TEF has no atresia but does have a tracheoesophageal fistula, which is often pretty high.
Type E EA/TEF is also known as H-type because of its anatomical appearance.
Type E (H-type) EA/TEF has the best results and is usually the easiest to fix.
Children with Type E (H-type) EA/TEF may present with symptoms later because they are still able to get solids and liquids down to the stomach and air to the lungs.