
Improving Outcomes for Congenital Diaphragmatic Hernia (CDH): Protocol Changes at Cincinnati Children's
With Dr. Paul Kingma · hosted by Dr. Jill Knerath
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
More about congenital diaphragmatic hernia
same diagnosisDive deeper → Congenital Diaphragmatic Hernia (21 items)Podcast
Stay Current Journal Club: Episode 1 - Ventricular Dysfunction in CDH and...
16 min · Published Feb 2021
Video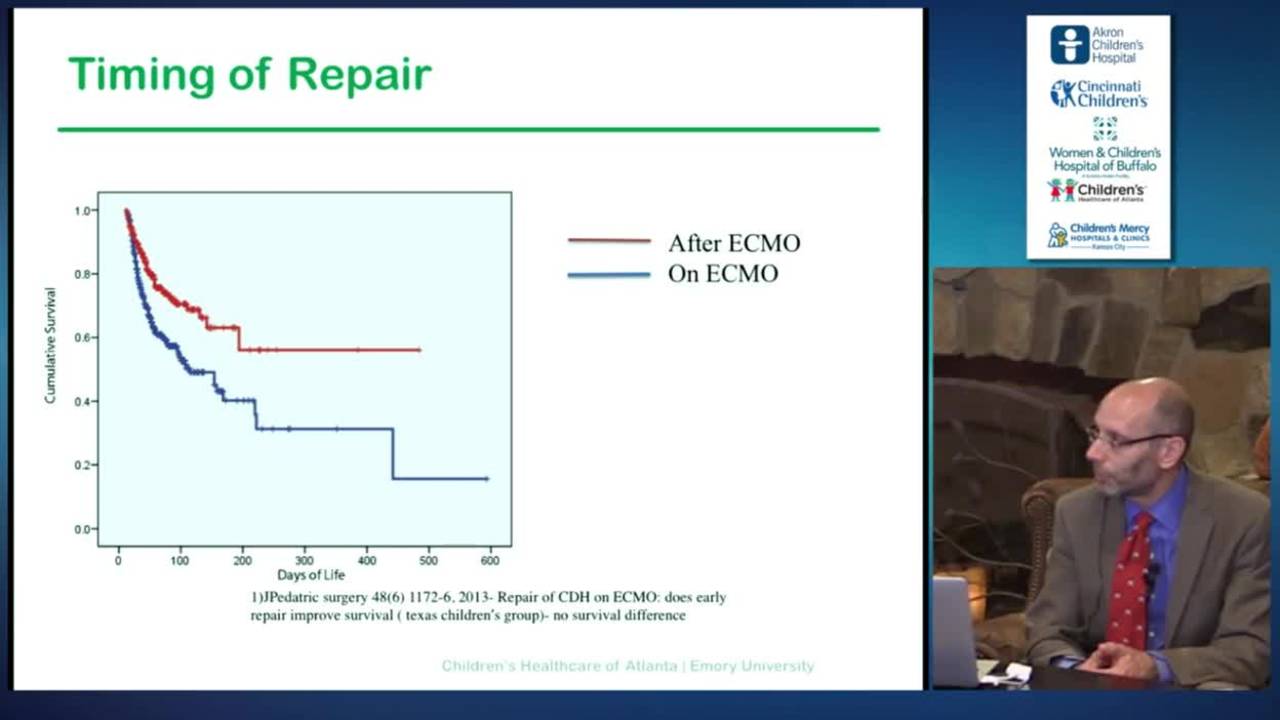
CDH-ECMO - VV vs. VA - Repair on ECMO: Update Course 2015
10 min · Published Nov 2015
Video
CDH-ECMO Routine Patient Preoperative Workup, Timing, Technique: Update...
3 min · Published Nov 2015
Video
EUPSA - Circular RNA profiles isolated from amniotic fluidscan distinguish between CDH survivors and non-survivers - Richard Wagner
9 min · Published May 2022
Video
Best of the Best in Pediatric Surgery Winner Announcement
8 min · Published Apr 2022
Video
CDH - MIS vs. Open: Update Course 2015
5 min · Published Nov 2015
Only a few other public items share this expert — go deeper there →
What the experts said
Initial protocol focus was on delivery room, ECMO utilization, and ventilator management, then progressed system by system through GI, cardiac, and neuro
Previously, for non-ECMO patients, surgical repair was performed when echocardiography demonstrated improved pulmonary hypertension, ranging from a few days to as late as 56 days
Under the new protocol, all ECMO patients are repaired within the first 12 to 24 hours of ECMO cannulation
All non-ECMO patients are repaired between day 4 and 8, provided they are stable, which applies to the vast majority
The clinical philosophy is that if you protect the lungs, all the rest will fall in line and improve
The new protocol never exceeds a peak pressure of 22 cmH2O
A standardized escalation and weaning protocol is followed approximately 100% of the time
Every baby now gets started on hydrocortisone for blood pressure support
There is a standardized protocol for which pressors are used
Inhaled nitric oxide is only started if there is evidence of a need
The All Children's philosophy is that starting NG feeds before oral feeding capability causes babies to lose the developmental connection between oral feeding and satiety
Babies are not fed enterally until they can feed by mouth; prior to that they receive TPN
Every baby now gets started automatically on a continuous sedation drip
Overall use of sedation has plummeted since starting universal continuous drips despite starting at a higher baseline level
After protocol implementation, the patient population appears to be skewed to the extremes with slightly more severe and slightly more mild cases
Survival increased from around 70% to around 80% after implementing protocol changes
Median time on mechanical ventilation dropped from 19 days to 9 days, almost a 50% decline
The philosophy of getting babies on ECMO sooner has not caused an increase in the number of ECMO babies
There are many problems that CDH babies have beyond survival that need improvement
Protocol changes began in August 2023 and were implemented in spring of 2024
Previously, peak pressures were limited to 25 to 26 cmH2O and mean airway pressures to less than 16 to 17 cmH2O
Previously, babies were fed once they had return of bowel function after repair
Previously, babies received as-needed sedation
The new cohort had 36 babies compared to 99 in the previous cohort
ECMO use increased from 14% to 22% in the new cohort
Survival for ECMO patients increased from 39% to 55%
ECMO use was around 41% in the old cohort versus 45% in the new cohort