


Chapter 1 of 6 · Surgical Management
Setup & positioning
Room setup, patient positioning, and trochar placement
Expert statements on this page
No expert statements were drawn from this page.
Host summaries · secondary, not cited in answers
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video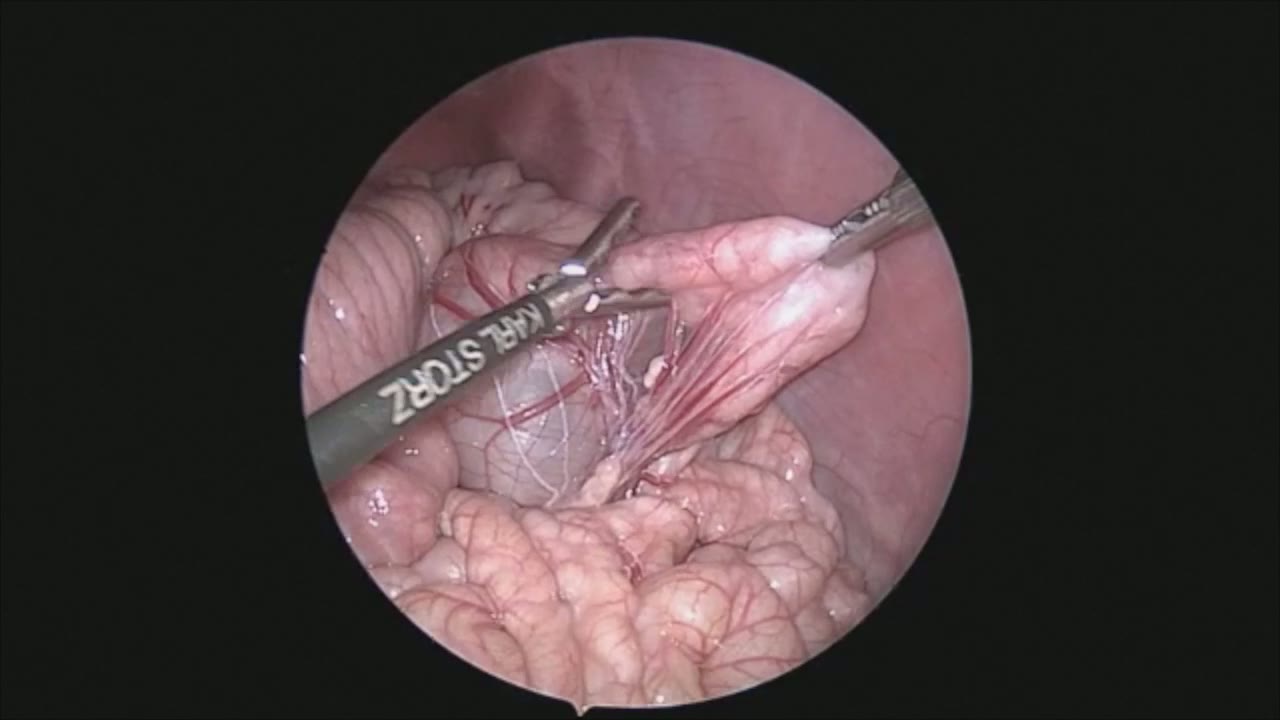
sealer demo
Dr. Steve Rothenberg · 3 min · Published May 2026
Video
pyloric knife
Dr. Steve Rothenberg · Published May 2026
Video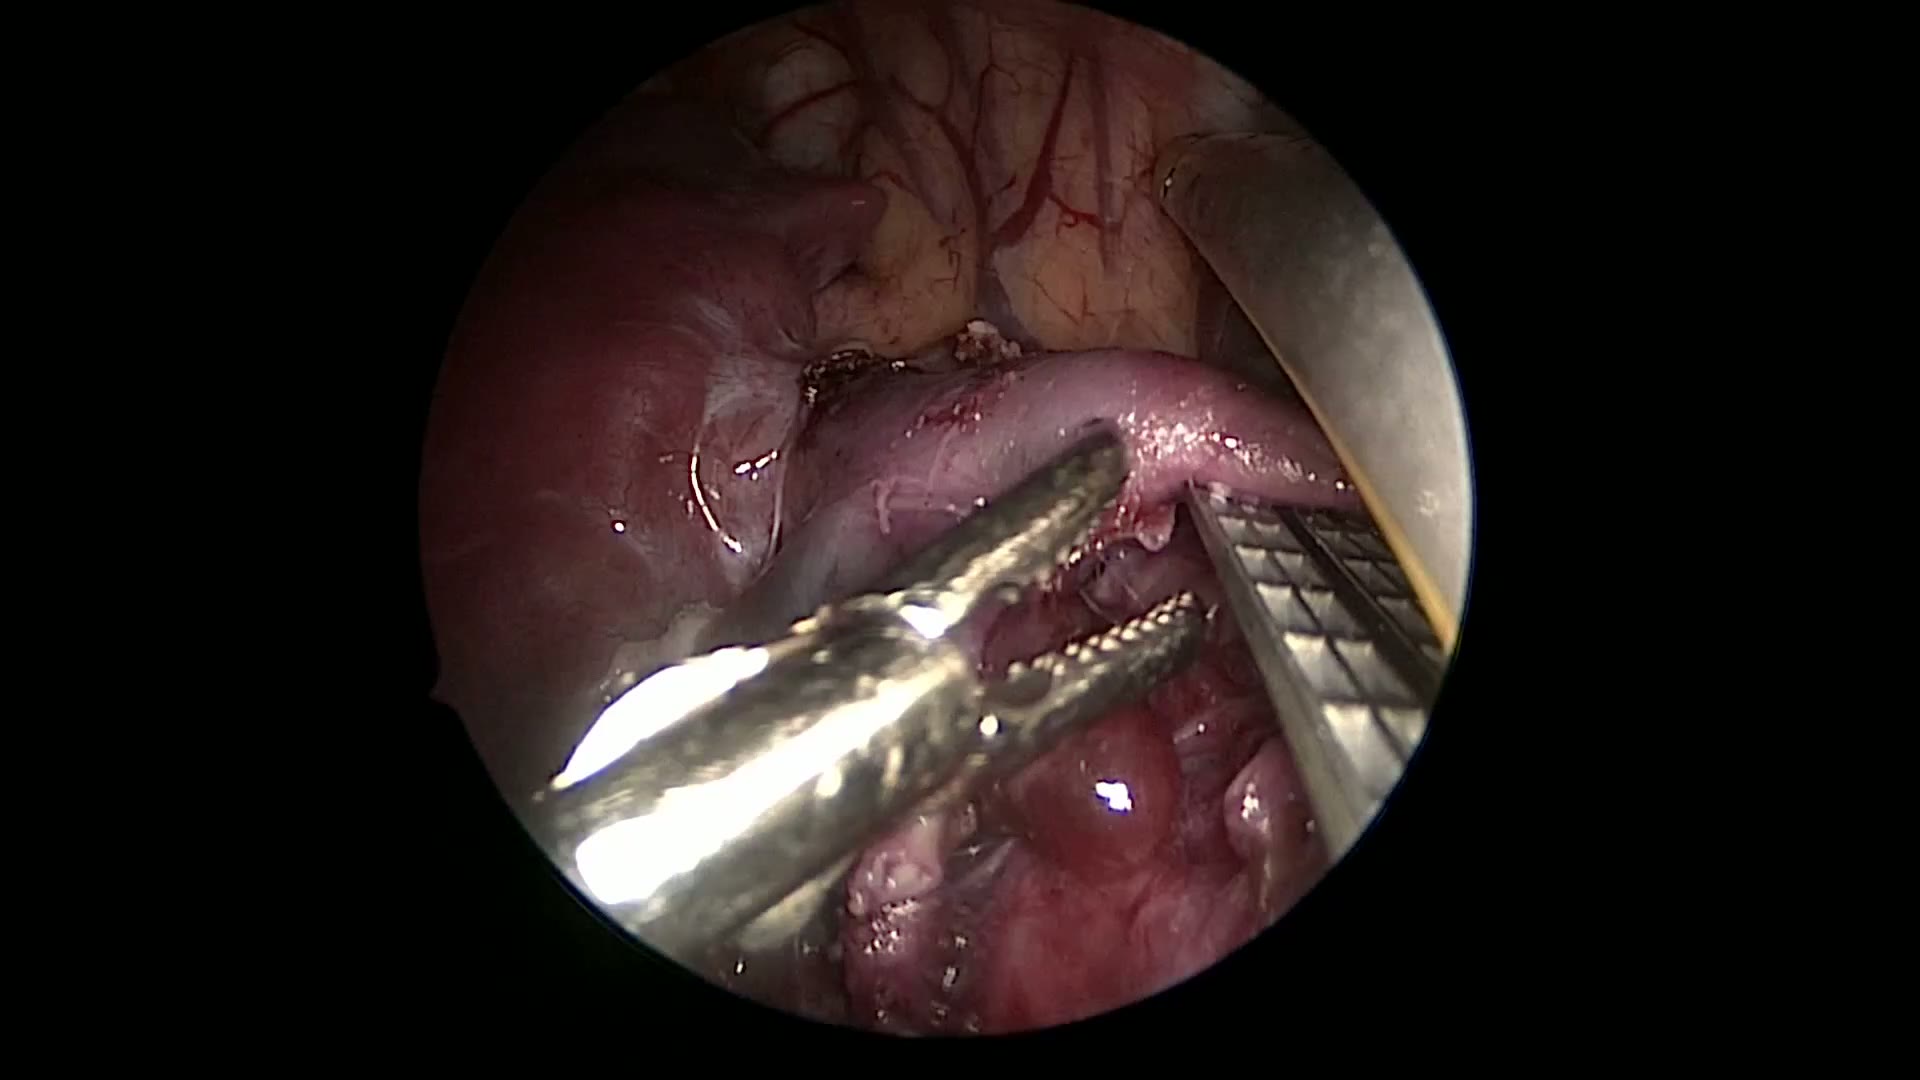
pulm artery LLL
Dr. Steve Rothenberg · 9 s · Published May 2026
Video
plication narrated
Dr. Steve Rothenberg · 6 min · Published May 2026
Video
percuvance redo nissen
Dr. Steve Rothenberg · 5 min · Published May 2026
Video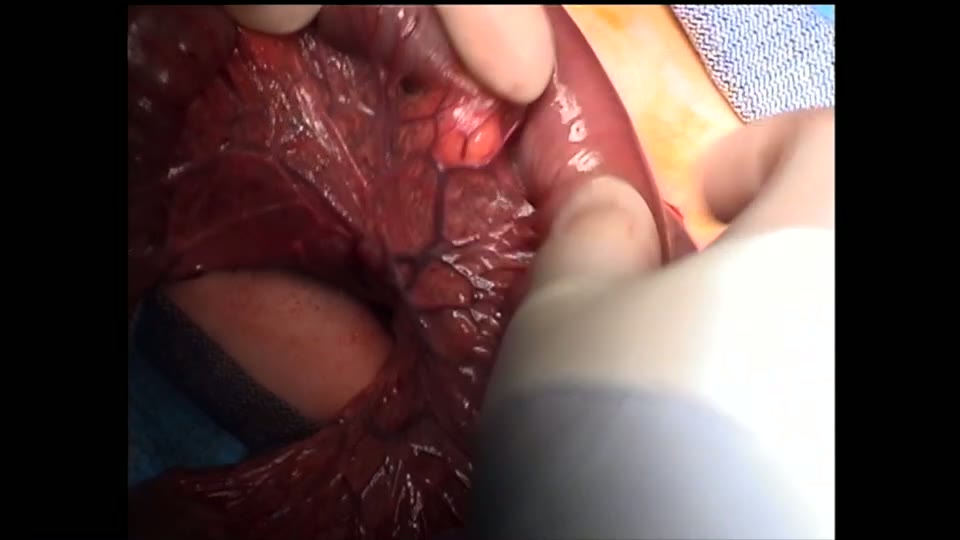
open bowel anast
Dr. Steve Rothenberg · Published May 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
The azygos vein in this case was approximately 4 millimeters in diameter and was sealed proximally and distally with the 3 mm sealer before sharp division.
The sealer provides excellent hemostasis with little risk of bleeding or other issues when dividing the azygos vein.
Lung collapse was achieved by insufflating CO2 at a pressure of 4 at a flow of approximately 1 liter per minute, without main stem intubation.
The fistula entered the carina right at the bifurcation, described as a trifurcation fistula, meaning the gap was much larger than initially thought because of the low entrance at the bifurcation.
A 5 millimeter endoscopic clip was used to secure the fistula, which the surgeon prefers to suture ligation as it provides a very atraumatic and quick way to secure the fistula.
The gap appeared to be approximately 4 vertebral bodies.
Dissection between the membranous wall of the trachea and the esophageal pouch is often difficult due to dense connective tissue in this area.
This portion of the dissection is much safer with the sealer than with a hook cautery as previously used.
The sealer allows dissection well up into the thoracic inlet and neck, with the dissection in this case extending well up into the neck.
The lower pouch tends to retract once the fistula is divided, making it more difficult to find, so division is delayed until ready to perform the anastomosis.
The anterior and posterior vagus nerves are carefully dissected off the esophagus during lower pouch mobilization to prevent injury to these structures.
The tip of the upper pouch is generally completely amputated to ensure a good ostium for the anastomosis.
The initial back wall stitch is placed using a knot pusher because of the significant tension on the two ends.
The back row sutures are placed going from inside out on the upper pouch to outside in on the lower pouch, with 4 to 5 stitches typically used.
The rest of the sutures after the initial stitch are tied intracorporeally to minimize pulling or stress on the soft esophageal walls.
Generally 4 to 5 throws are placed to secure an adequate knot.
The true key to this operation is mobilization of the upper pouch, and the use of the sealer allows very safe dissection well up into the neck.
The surgeon easily doubled the length of the upper pouch available by doing extensive dissection up into the neck in this case.
The visualization of the upper pouch dissection thoracoscopically is much greater than when trying to perform this through an open thoracotomy.
The nasogastric tube is left for 4 to 5 days and removed on the 4th postoperative day when a contrast study is obtained to ensure there is no leak.
This procedure took 75 minutes and the child tolerated the surgery extremely well.
The child had no other congenital anomalies.
A contrast study obtained on the 4th postoperative day showed no evidence of leak and feeds were started.
The child was on full feeds by the 8th postoperative day.
The child maintained saturations in the mid-90s throughout the procedure with end-tidal CO2s around 40.
The child did not have single lung ventilation but had a tracheal intubation which was well tolerated.