
The Colorectal Quiz Episode 4
With Dr. Mark Levitt & Dr. Jason Frischer & Dr. Andrew Badillo & Dr. Aaron Garrison · hosted by Dr. Rod Gootee & Dr. Todd Ponsky · Marc Levitt
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Podcast
The Colorectal Quiz Episode 4: Classic Hirschsprung disease - Surgical Technique
19 min · Published Feb 2021
Podcast
The Colorectal Quiz Episode 3.5: Proximal Hirschsprung Disease
8 min · Published Feb 2021
Video
Hirschsprung Disease: Update Course 2015
CCHMC Pediatric Surgery · 7 min · Published Nov 2015
Video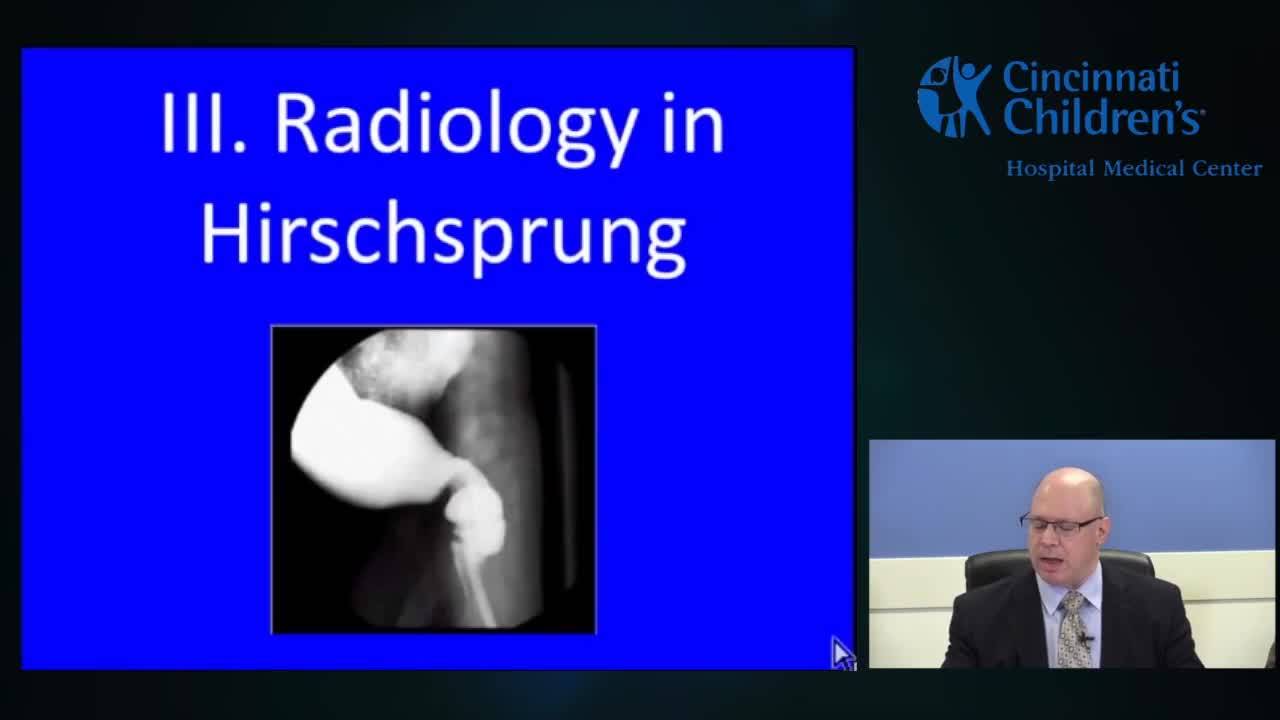
Evaluation & Management Of Hirschsprung's Disease
44 min · Published Nov 2018
Video
Panel Discussion and Case Presentation Part II: Pediatric Bowel Management 2013
Dr. Todd Ponsky · 33 min · Published May 2013
Video
Total Colonic Hirschsprung Disease with Malrotation: Difficult Cases
13 min · Published Dec 2013
Podcast
(500) Days of Summer (classic Movie Review: Zooey Deschanel, Joseph Gordon-Levitt, Marc Webb) by The Cory Baker Show
Marc Levitt · Published Aug 2026
Video
Meeting with Marc Levitt: Clinical Discussion with Ivon Martinez
Marc Levitt · Published Jul 2026
Video
Introducing Dr. Marc Levitt: Pediatric Colorectal Surgeon Profile
Marc Levitt · Published Jul 2026
Video
Integrated Care Concept in Pediatric Colorectal Surgery by Marc Levitt
Marc Levitt · Published Jul 2026
Video
Patient Outreach and Communication in Pediatric Colorectal Surgery
Marc Levitt · Published Jul 2026
Video
Keynote Address on Pediatric Colorectal Surgery by Dr. Marc Levitt
Marc Levitt · Published Jul 2026
Podcast
Colorectal Quiz: Episode 49 - Collaborating for Kids: Colorectal & Pelvic Solutions (with a Little Help from AI)
Marc Levitt · 40 min · Published Jul 2025
Podcast
Colorectal Quiz: Episode 49 – Collaborating for Kids: Colorectal & Pelvic Solutions (with a Little Help from AI)
40 min · Published Jul 2025
Podcast
Colorectal Quiz: Episode 46
Marc Levitt · 29 min · Published Apr 2025
Podcast
Colorectal Quiz: Episode 46
Marc Levitt · 29 min · Published Apr 2025
Podcast
Colorectal Quiz: Episode 43
Marc Levitt · 23 min · Published Jan 2025
Podcast
Colorectal Quiz: Episode 43
Marc Levitt · 23 min · Published Jan 2025
Video
Dr. Marc Levitt on the CTO Mission in Pediatric Colorectal Surgery
Marc Levitt · Published Jul 2026
Video
Addressing Ministers of Health: Pediatric Colorectal Surgery Advocacy and Global Healthcare Priorities
Marc Levitt · Published Jul 2026
Video
Andrea Kesar Discusses Marc Levitt's Contributions to Pediatric Colorectal Surgery
Marc Levitt · Published Jul 2026
Video
Introduction to Dr. Marc Levitt's Pediatric Colorectal Surgery Practice
Marc Levitt · Published Jul 2026
Video
The History of International Colorectal Surgery Team Development
Marc Levitt · Published Jul 2026
Podcast
Hirschsprung's Disease with Dr. Marc Levitt
Marc Levitt · 22 min · Published Jul 2026
What the experts said
Laparoscopic approach allows ability to biopsy elsewhere if transition zone is not rectosigmoid
Deep laparoscopic dissection into pelvis minimizes transanal work needed and avoids sphincter overstretching morbidity
Transanal dissection should take under one hour in primary pull-through
Full-thickness biopsy must include seromuscular side same size as mucosal side (cube-shaped)
Should wait for frozen section before taking mesentery
Adequate frozen section requires ganglion cells and nerves less than 40 microns
Frozen section biopsy must include submucosa to avoid missing hypertrophic nerves in submucosal layer while finding ganglion cells in seromuscular layer
Mesenteric dissection should stay close to bowel wall, not deep in mesentery, to reduce bleeding
In old Swenson procedures done through abdomen, too wide distal rectal dissection caused incontinence and urinary retention from nerve injury
Must preserve arcade along left colon and sigmoid to get enough length to reach pelvis
For distal disease, can take just distal IMA branches; for left colon disease may need to take IMA to get splenic flexure to reach
Transanal dissection should start about one centimeter above dentate line
Swenson full-thickness dissection follows areolar plane which is essentially bloodless
Soave submucosal dissection leaves a cuff; if performed, cuff should be very short (about one centimeter) and must be split
Resection margin should be approximately five centimeters above biopsy site where bowel looks good
Tacking sutures from serosa to pelvic sidewall at three and six o'clock positions anchor anastomosis in place
Reinforcement layer is critical to line up bowel pieces for mucosa-to-mucosa anastomosis