
Gastroschisis - Clinical Practice Updates
With Dr. Miguel Gilfoid · Live Event Content
Cued at 23:21 · stops at 24:06 · press play
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Podcast
Abdominal Wall Defects with Dr. Jacob Langer
52 min · Published Dec 2016
Video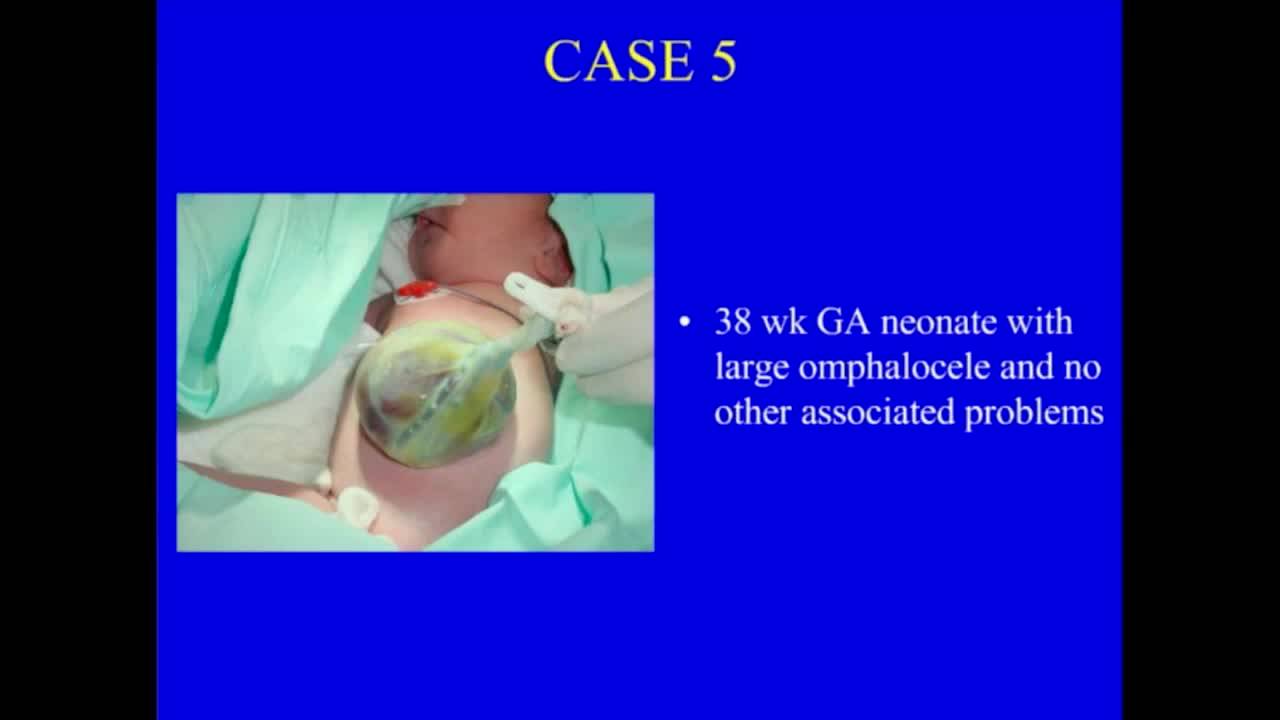
Abdominal Wall Defects
37 min · Published Nov 2018
Video
Abdominal Wall Defects: Update Course 2013
37 min · Published Sep 2013
Podcast
Abdominal Wall Defects with Dr. Jacob Langer
52 min · Published Dec 2016
Podcast
Malrotation with Dr. Meera Kotagal
13 min · Published May 2023
Video
Omphalocele & Gastroschisis
Dr. Todd Ponsky · 9 min · Published Mar 2022
Only a few other public items share this expert — go deeper there →
Video
Mental Health and Gun Safety in Pediatrics - Catherine Neyer - APP Conference 2026
48 min · Published May 2026
Video
Overview of the Surgical Management of Acute and Chronic Pancreatitis in Children with Dr. Juan Gurria
66 min · Published Apr 2026
Video
Clinical & Research Update: Pediatric Liver Tumors - A Case-Based Discussion with Drs. Katherine Somers & Alex Bondoc
69 min · Published Apr 2026
Video
Beyond ChatGPT_ AI Tools You’re Not Using (But Should) - Vail, CO
Dr. Todd Ponsky · 97 min · Published Jan 2026
Video
Beyond ChatGPT: AI Tools You’re Not Using (But Should)
Dr. Todd Ponsky · 109 min · Published Oct 2025
Video
2025 Pediatric Surgery Update Course - Updates in Lap Chole and Cholecystitis Management
18 min · Published Aug 2025
What the experts said
Giant omphalocele (≥5 cm or liver in sac) patients had greater time to full feeds, required more TPN, had greater risk of respiratory insufficiency, and higher incidence of chromosomal anomalies compared to routine omphalocele in a two-center 20-year retrospective study of 97 survivors.
56 of 97 giant omphalocele patients were identified as having pulmonary hypertension, with most diagnosed within the first week of life.
Five patients with giant omphalocele had no signs of pulmonary hypertension on initial echo within first seven days but subsequently developed severe pulmonary hypertension after sepsis episodes, with two deaths and one requiring pulmonary vasodilator for more than a year.
One patient developed severe pulmonary hypertension 52 days after initial echo showed no pulmonary hypertension, triggered by a single episode of sepsis.
The sac-preserving active reduction technique developed by Dr. Abello from Colombia has been used in almost 40 patients over three years by Miguel Gilfoid's group.
Using the sac-preserving technique with hydrocolloid dressing, 97% of patients achieved closure within 30 days and 92% within 15 days.
All patients treated with the sac-preserving technique are kept in ICU, ventilated and completely paralyzed during the reduction process.
The hydrocolloid dressing should ideally be applied within the first 24 hours after birth so the sac doesn't become very stiff, and it keeps the sac very smooth and hydrated.
Three patients with ruptured omphalocele sac at birth were sutured and then had the hydrocolloid dressing applied successfully.
Compressions can usually start within 48 hours after hydrocolloid application once the baby is stable.
In a study by Amy Wegner comparing omphalocele and gastroschisis, gastroschisis had higher risk of adhesive bowel obstruction, but omphalocele had higher risk of midgut volvulus.
Patients with omphalocele have non-rotation or malrotation and will not have the same adhesions as gastroschisis patients.
If the surgical technique for omphalocele closure involves exposing the intestines, it may be worth considering a Ladd procedure, but not worth going through the sac if the technique maintains the sac.
During diaphragmatic hernia repair, the key move to decrease volvulus risk is to unroll the cecum and proximal bowel if they are rolled together like a scroll, ensuring small bowel is to the right, colon to the left, and anterior surface of mesentery is exposed.
Non-rotation does not exclude the possibility of having anatomy with a narrow base of mesentery and the two ends being fairly close together, creating volvulus risk.
In gastroschisis, the liver is not expected to be herniated outside the abdomen.
For massive abdominal wall defects where there is no amnion and nothing to sew, Miguel Gilfoid uses a prolene mesh that stays in place until closure can be achieved, protecting it with a plastic bag around the bowel.
With giant abdominal wall defects, when a spring-loaded (tech) silo is placed and pushed down, the forces go outward and can actually make the defect much bigger over time.
Biologic mesh can be used as a scaffold that sticks to the bowel and allows skin to epithelialize over massive defects.
Miguel Gilfoid reports that 80% of massive gastroschisis cases can be closed within two to three months using prolene mesh that remains in place for months.
Component separation technique involves separating tissue at the external oblique about a centimeter beyond the rectus sheath bilaterally, then dissecting between external oblique and the transversus/internal oblique, which creates substantial room for closure.
An incision on top of the anterior rectus sheath can provide another centimeter of advancement during component separation.
Tissue expanders placed inside the belly without any domain would push all contents up and out rather than creating useful space, according to plastic surgery colleagues.
A group from UT Houston (Cogen, Rich, and Recy) reported using component separation in nine children aged 7 days to 10 years, majority with omphalocele and giant defects, achieving fascial closure in almost every case, with some requiring mesh to bridge defects.