
Topics in 10: Wilms Tumor
With Dr. Andrew Davidoff · StayCurrentMD
Cued at 0:28 · stops at 1:13 · press play
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video
Wilms Tumor
Published May 2020
Video
Wilms Tumor Protocol Violations: Practice Gap discussion at Update Course 2018
9 min · Published Aug 2018
Podcast
Wilms Tumor: Audio Chapter
64 min · Published Jun 2017
Video
Wilms Tumor Protocol Violations: 2018 Pediatric Surgery Practice Gap #3
Dr. Todd Ponsky · Published Jun 2019
Podcast
Wilms Tumor: Audio Chapter
64 min · Published Jun 2017
Video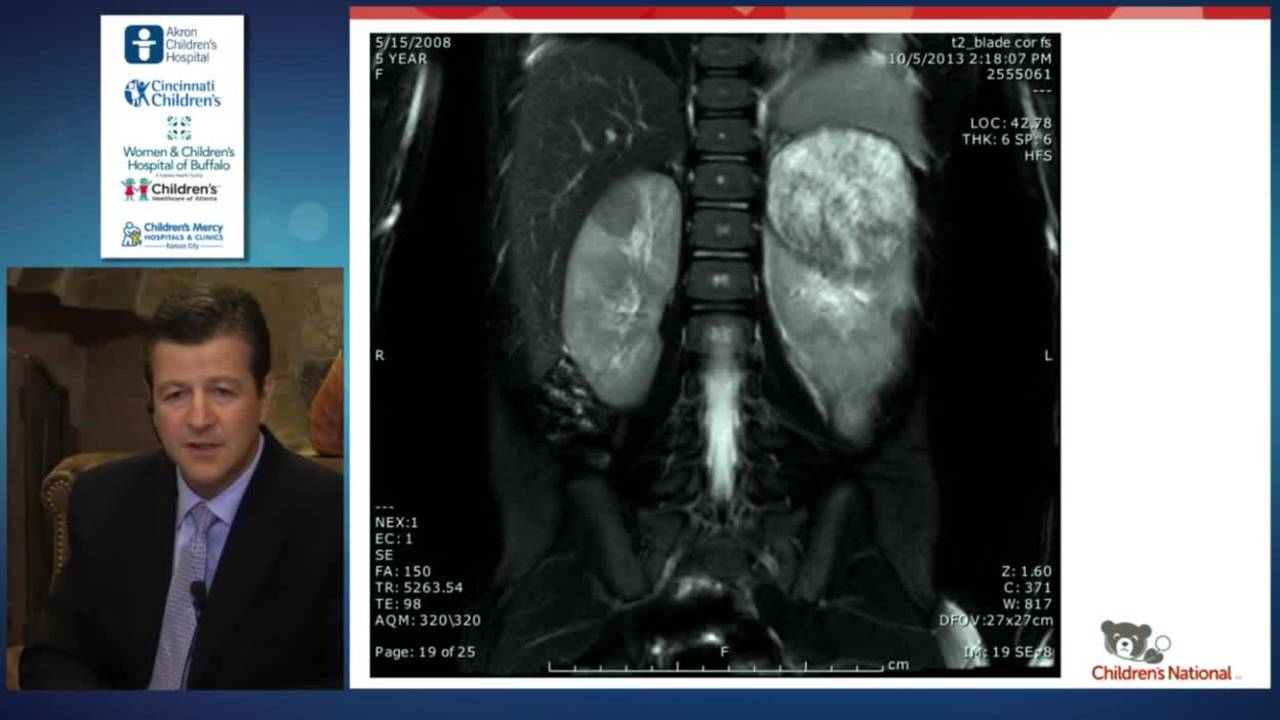
Wilms Tumor Rapid Fire: Update Course 2015
8 min · Published Nov 2015
Only a few other public items share this expert — go deeper there →
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
Approximately 75% of Wilms tumor cases occur in children younger than 5 years of age, with a peak incidence at 2 to 3 years of age.
Survival for patients with Wilms tumor, when considered as a whole, is currently greater than 90%.
Histology is a critical prognostic factor that profoundly impacts outcome in Wilms tumor, divided into favorable and unfavorable (anaplastic) histology.
Anaplastic histology comprises only about 10% of Wilms tumor cases but contributes to over 50% of Wilms tumor mortality.
Children with Wilms tumor typically present with an asymptomatic abdominal mass.
Associated signs and symptoms such as malaise, pain, microscopic or gross hematuria are found in only about 25% of children with Wilms tumor, as is hypertension.
The workup of a child with an intra-abdominal mass suspected of being Wilms tumor usually begins with ultrasound.
CT of the abdomen and pelvis is generally the definitive imaging study of choice for patients suspected of having a renal tumor based on ultrasound.
CT will confirm the presence of a solid renal mass and afford the opportunity to visualize the contralateral kidney to confirm its presence and function and to exclude synchronous bilateral disease.
Intravascular tumor extension occurs in about 6% of Wilms tumor cases.
Intravascular tumor extension should be specifically investigated in preoperative evaluation as it may alter the timing and conduct of surgery.
If intracardiac extension of tumor thrombus is suspected, this can be assessed by echocardiography.
The most common site of metastatic spread of Wilms tumor is the lungs.
A chest CT should be included in the initial evaluation of a child suspected of having Wilms tumor.
The Children's Oncology Group uses a surgical pathologic staging system in which localized Wilms tumors confined within the renal capsule are stage 1.
Wilms tumors that penetrate the renal capsule but are resected with negative margins are stage 2.
Circumstances that make Wilms tumor stage 3 include biopsy or rupture (preoperative or intraoperative), positive resection margin or gross residual disease, lymph node involvement, or the administration of preoperative chemotherapy.
Metastatic disease, which occurs in about 12% of Wilms tumor patients, is considered stage 4.
For stage 4 disease, the local stage should also be evaluated as this will determine whether abdominal radiation is indicated and to what field.
Patients with synchronous bilateral Wilms tumor are stage 5, but local stage for each side should still be evaluated.
For unilateral tumors, upfront resection with regional lymph node sampling (generally radical nephrectomy) is currently the recommendation from the Children's Oncology Group.
Although Wilms tumors can grow to a large size, even large tumors rarely invade surrounding structures, so most Wilms tumors are resectable at presentation.
Failure to perform upfront resection but instead administering neoadjuvant chemotherapy in the COG results in classification of a tumor as stage 3, thus mandating the use of flank irradiation and doxorubicin, each associated with significant long-term toxicities.
Treatment of favorable histology Wilms tumor stage 1 or 2 is limited to vincristine and actinomycin D.
In rare circumstances when the tumor is stage 1, weighs less than 550 grams (tumor weight plus kidney), and the patient is less than 2 years of age, no adjuvant chemotherapy is given.
Raising the age and weight limits for observation without adjuvant chemotherapy are currently being considered for study by COG.
Careful lymph node sampling is a critical part of any operation for Wilms tumor because the presence of nodal involvement is associated with an increased incidence of tumor relapse and a poorer prognosis.
Lymph node sampling should be performed even in the absence of abnormal nodes on preoperative imaging or on gross inspection during operative exploration, since these circumstances don't reliably predict lymph node negativity.
Partial nephrectomy for patients with unilateral, non-syndromic disease and laparoscopic nephrectomy are not currently standard of care and should generally only be performed in the context of a clinical trial.
Anaplastic histology is associated with a significantly worse outcome and is treated with more intensive chemotherapy.
A distinction is made between focal and diffuse anaplasia when determining specific adjuvant therapy.
About 5% of children with Wilms tumor will present with synchronous bilateral disease or stage 5 disease.
Children with bilateral Wilms tumor receive neoadjuvant chemotherapy with three drugs (as used for stage 3 or 4 favorable histology) to shrink tumors prior to surgery and facilitate preservation of normal renal parenchyma, due to increased risk of renal failure.
Patients with Wilms tumor arising in a solitary kidney or those with unilateral Wilms tumor at increased risk for developing metachronous tumor are also treated with neoadjuvant chemotherapy, though these patients usually don't receive doxorubicin.
A biopsy is not required in children with bilateral solid renal masses as bilateral Wilms tumor is the very likely diagnosis.
Studies have shown that biopsies of bilateral renal masses rarely detect anaplasia even when it does exist in the tumor mass.
A biopsy, if performed in bilateral disease, doesn't mandate subsequent radiation as it does in patients with unilateral Wilms tumor.
Bilateral nephron-sparing surgery should be considered in all patients with bilateral Wilms tumor and should be performed after either 6 or 12 weeks of neoadjuvant chemotherapy.
Longer courses of preoperative chemotherapy (beyond 12 weeks) are definitely discouraged in bilateral Wilms tumor.
It should be determined by preoperative imaging whether there is intravascular tumor extension, then its presence or absence confirmed intraoperatively.
Tumor extension into the renal vein and proximal inferior vena cava can in most cases be removed en bloc with the kidney and tumor.
Thrombus that extends further into the vena cava can be withdrawn from the IVC after gaining proximal and distal control.
Proximal control can generally be achieved if the superior extent of the thrombus is below the level of the hepatic veins.
Primary resection of tumors with extension above the level of the hepatic veins or especially into the atrium is associated with higher operative morbidity, so neoadjuvant chemotherapy is generally used in these circumstances.
Thrombus that extends above the hepatic veins and persists to this extent after neoadjuvant chemotherapy probably requires cardiopulmonary bypass to safely remove the full extent of disease.
About 12% of Wilms tumor patients will have evidence of hematogenous metastases at diagnosis with 80% of these being pulmonary metastases.
A new response-based approach is being used for patients with stage 4 disease in the Children's Oncology Group.
Stage 4 patients treated with three-drug chemotherapy who have radiographic disappearance of their lung metastases or tissue confirmation that residual nodules don't contain viable tumor at week 6 imaging re-evaluation will be considered rapid responders, will continue on three-drug chemotherapy, but won't receive pulmonary irradiation.
Patients who don't have complete resolution of pulmonary nodules at 6 weeks will be considered slow or incomplete responders, will be switched to more intensive chemotherapy regimen, and will receive whole lung irradiation.
Wilms tumor is the second most common intra-abdominal tumor in children and fifth most common tumor in children overall.