
Hirschsprung Disease: Radiology Aspect
With Dr. Rodrigo Ocelami · hosted by Dr. Todd Ponsky & Dr. Em Gootee · StayCurrentMD
Cued at 15:49 · stops at 16:34 · press play
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video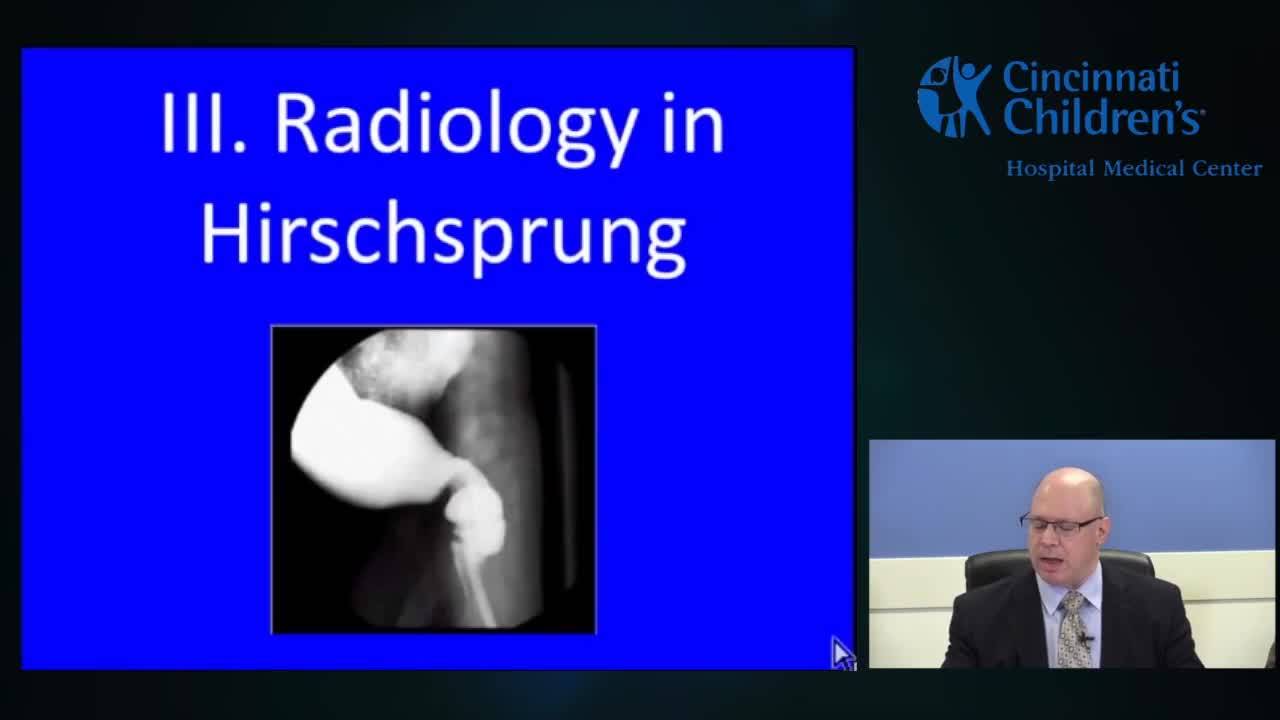
Evaluation & Management Of Hirschsprung's Disease
44 min · Published Nov 2018
Video
Radiology and Image Diagnosis of Hirschsprung Disease
44 min · Published Nov 2018
Video
Contrast Enema for Hirschsprung Disease
11 min · Published Feb 2015
Video
Outcomes and Complications in Hirschsprung Disease
105 min · Published Nov 2018
Podcast
Colorectal Quiz Episode 3: Hirschsprung Disease
20 min · Published Feb 2021
Video
Hirschprung's Disease - Daniel von Allmen
38 min · Published Nov 2018
Only a few other public items share this expert — go deeper there →
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Update Course Rewind 2025: Hirschsprung + ARM: Rare but Real
1 min · Published May 2026
Video
Pooling Patients to Study Rare Pediatric Tumors: An Introduction to PSORC
56 s · Published May 2026
Video
The fetal frontier: A review of current and emerging fetal therapies for genetic diseases
44 s · Published May 2026
Video
Indocyanine green assists with sentinel lymph node mapping in pediatric and adolescent patients
1 min · Published May 2026
What the experts said
In the 1960s and 1970s fluoroscopy was done by everybody and done very well, but with the advent of MRI, CT, and ultrasound there has been a shift to more current modalities and fluoroscopy is almost a lost art.
In a newborn on plain radiograph you cannot tell the difference between colon and small bowel; you can only say there are multiple dilated loops suggesting distal bowel obstruction.
The differential diagnosis for neonatal distal bowel obstruction includes Hirschsprung disease, small left colon syndrome (meconium plug syndrome, immature colon), anorectal malformation, meconium ileus, and ileal atresia, which together account for about 99% of cases.
Seeing air in the rectum on plain radiograph does not rule out Hirschsprung disease.
The radiological diagnosis of enterocolitis is possible with a plain abdominal radiograph.
Air-fluid levels visible in the colon on cross-table or decubitus views are a sign of inflammatory process, potentially enterocolitis.
Enterocolitis in a newborn should be considered Hirschsprung disease until proven otherwise.
Repeat enemas in patients with long segment disease are futile and will not provide better localization of the transition zone.
In patients with longer segment disease, surgeons should plan the operation assuming the transition may be high rather than relying on the enema findings.
Insert the rectal tube only 2 to 3 centimeters into the rectum for contrast enema.
Never use a Foley catheter inside the rectum for contrast enema in suspected Hirschsprung disease.
In the neonatal period, use water-soluble contrast diluted 50% with saline for contrast enema.
Inject contrast very slowly and gently via syringe (not gravity) to avoid distending the aganglionic segment and missing the diagnosis.
After the neonatal period, fill only up to the transverse colon; if the studied segment appears normal in distension, caliber, and mucosa, and the splenic flexure shows no suggestion of total colonic involvement, stop at the transverse colon.
Obtain two images in left lateral decubitus, two in right lateral decubitus, and two in AP position during contrast enema.
The inversion of the rectosigmoid index (rectum smaller than sigmoid) is very helpful in diagnosing Hirschsprung disease.
The affected (aganglionic) segment will be spastic, which is why contrast should not be given in large amounts or too fast, as this will cause you to miss the spasticity.
Always counsel families about good hydration after contrast enema to help the child evacuate the contrast and avoid dehydration.
Show the family the contrast material before and after the study so they know what to expect when white material comes out.
The water-soluble iodinated contrast used for enemas has an osmolality of about 400, similar to colon-cleansing agents, and is hyperosmotic.
The hyperosmotic contrast not only helps make the diagnosis but also attempts to clean the colon.
If contrast stays in the colon, neonates can become dehydrated, so the neonatal ICU must be informed.
Use gravity infusion from a bag with large IV tubing at a moderate pace (not slow) to rapidly show both distal and proximal segments and visualize the transition zone quickly.
Early maximal distention is best for seeing the transition zone; waiting too long can cause distention of the distal aganglionic segment because it is soft tissue, not a rigid pipe.
If the colon looks small in a neonate, fill the entire colon and attempt to reflux into the terminal ileum to make other diagnoses if present.
In a full-term infant, use a 12 to 14 French Foley catheter; in a premature infant, use a smaller size.
A true lateral image with femurs superimposed is essential to visualize the presacral space properly.
On frontal view, ensure the tube is visible but also visualize distal to it to avoid missing a very distal transition zone.
In a normal neonate, the proximal colon toward the splenic flexure is always a little smaller than the rectum.
If a Foley catheter balloon is inflated in the rectum to prevent leakage, it will miss very short segment Hirschsprung disease every single time.
Contrast enema in premature infants does not follow the rules; the colon can look immature and small, making it difficult to distinguish from Hirschsprung disease.
Contrast enema can be performed in premature infants as young as 35 to 36 weeks gestational age with reasonable diagnostic accuracy.
Below 35-36 weeks gestational age, when necrotizing enterocolitis becomes more prevalent, diagnostic accuracy of contrast enema decreases.
The rectosigmoid transition in Hirschsprung disease is typically at the S2 level; if distal to S1-S2 it is considered distal rectal, if more proximal it is typical rectosigmoid.
Small left colon syndrome typically has a transition at the splenic flexure that is very abrupt.
The rectosigmoid index (rectum larger than sigmoid) is a good principle, but do not stop there—examine all the way up to the splenic flexure.
A case initially diagnosed radiologically as small left colon syndrome with transition at splenic flexure proved to be total colonic aganglionosis with transition in the terminal ileum.
If you have a proximal transition zone on enema, you cannot accurately determine where the pathologic transition actually is.
A proximal transition zone should prompt consideration of a more invasive surgical approach (laparoscopic or open) rather than transanal, because the true transition location is uncertain.
Rectal biopsy should be performed in almost any patient who needed a contrast enema to rule out distal obstruction, including cases of meconium plug or small left colon.
In clearly documented meconium ileus where reflux into terminal ileum is achieved and the patient clinically improves, rectal biopsy may not be necessary.
After Soave pull-through, contrast enema shows a wide presacral space due to the retained muscular cuff from partial-thickness dissection.
The widened presacral space after Soave is best seen on lateral view because the cuff extends circumferentially.
A true lateral view of the rectum is very important in post-surgical patients to assess for complications.
The Duhamel procedure creates a chimera of aganglionic segment distally with ganglionic segment proximally, not placed end-to-end or side-to-side but as a patchwork.
In symptomatic patients after Duhamel, an anterior pouch containing stool enlarges and impresses on the ganglionic bowel, causing obstruction.
In untreated Hirschsprung disease, even in patients 10, 12, 14, or 15 years old, a dilated rectum is never seen; by definition the aganglionic segment does not distend.
Patients who develop the characteristic Duhamel pouch with fecal impaction in the rectum may never have had true Hirschsprung disease, as the aganglionic rectum should not distend.
When resecting a Duhamel pouch, the specimen should be oriented and the pathologist alerted to determine whether ganglion cells are present in the rectum.
Resected Duhamel pouches have been observed to contain both ganglionic and aganglionic parts.
A contrast enema showing dilated, redundant colon filled with stool but normal rectum and presacral space represents idiopathic constipation, not Hirschsprung disease.
In a patient with a contrast enema showing dilated colon and normal rectum, rectal biopsy is a waste of time because the patient does not have Hirschsprung disease.
If a biopsy is taken in functional constipation, there is risk of obtaining an aganglionic result from the normal physiologic aganglionic zone, which does not mean the patient has Hirschsprung disease.
There is no way to differentiate so-called ultra-short segment Hirschsprung disease from idiopathic constipation.
The rectum has a normal area with ganglion cells, then a zone with no ganglion cells (normal physiologic aganglionosis), but the length of this aganglionic zone has never been accurately determined at different ages.
There is no accurate study defining the length of normal physiologic aganglionosis in preterm infants, full-term babies, 6-month-olds, or older children—this is a challenge for young pediatric surgeons.
A biopsy taken in the zone of normal physiologic aganglionosis will show no ganglion cells but does not indicate Hirschsprung disease.
The internal sphincter has been defined as a thickening of the circular layer of normal smooth muscle bowel, but this thickening has never been personally observed in opened normal rectums at different ages.
If the internal sphincter thickening exists, nobody has determined the exact limit of that thickening at different ages.
Achalasia of the internal sphincter is a manometric concept, not an anatomic concept.